
Fat, Protein – Post Duodenal Switch Diet
May 23, 2016 6:43 am
Fat and Protein after weight loss surgery…. This is a subject that seems to come up all the time.
What I recommend is “…Water, protein, vitamins, supplements and every thing else….”
Dehydration can cause a lot of problems, stay hydrated.
Weight Loss Surgery (WLS) is a surgically imposed catabolic state (surgical induced starvation). The weight is lost by not allowing enough caloric intake/absorption and forcing the body rely on stored sources of energy, mostly fat mass. The rationale for the high protein intake is to minimize net muscle mass loss during the catabolic state. Low carbs and low fat further push the body into catabolizing the fat mass, and reducing the net loss of protein content. As the fat mass is broken down it will release hormones and other byproducts that the body will eliminate. Hydration is crucial to every bodily function and even more so in the weight loss phase to allow for elimination of some of these byproducts.
The mechanism by which Duodenal Switch works during the weight loss phase is by limiting the caloric intake. Long term Duodenal Switch keeps the weight off due to the malabsorptive component as the caloric intake increases. Protein intake, Vitamin/Mineral supplementation and diligence in surveillance of vitamin/mineral levels is imperative and a life long commitment after WLS.
There are a number of different types of Fatty Acids. Our bodies naturally produce, from other components, all but 2 essential fatty acids: Omega 3 and Omega 6. Most fatty acids require bile salts to be absorbed within the small intestines. Those are the fatty acids that are absorbed to a lesser degree after Duodenal Switch. Medium chained fatty acids do not require bile salts and can be absorbed into the blood stream from the small intestines. Medium chained fatty acids are used for energy as they are processed in the liver. Medium chained fatty acids are actually given to patients with Short Bowel Syndrome to decrease fatty stool and increase their body weight. This is also a possible reason some fats cause DS patients more loose stools and others do not (medium chained fatty acids). Adding fats is a purely individualized process. Each person has a different length of small bowel, alimentary limb, common channel, percentage of excess weight to lose and metabolism. Patient’s tolerance for fat in regards to vitamin/mineral levels, stool consistency and frequency is completely individualized.
Fats and Fatty acids can be divided according to their structure in groups:
A) Saturated Fat (animal fats, butter, lard- solid in room temperature)
B) Unsaturated Fat (liquid in room temperature)
The main focus in the weight loss phase should be hydration, hydration, hydration, protein, low carb, low fat and vitamin/mineral supplementation (page 22). Rest is key in the early post op phase but gradually adding exercise is also important in ensuring the body does not breakdown muscle mass. Adequate intake of protein and use of muscles diminishes the bodies natural response of breaking down muscle mass in a low caloric intake state.
Post Surgical Needs for the first 90 days in order of importance:
This is to allow healing to take place before adding additional stress on the body and surgical sites.
Minimum of 64 ounces of fluids daily
Minimum 80-100 grams of protein daily (protein requirements are based on ideal body weight)
30 gms by 30 days post-op
60 gms by 60 days post-op
90 gms by 90 days post-op
Vitamin/Mineral Supplements
Low carb
Low fat
Rest (early Post-op)
Exercise
Proteins are important, not only for structure (muscle) but for functions. We know that proteins and amino acids are involved in all aspects of our body’s function. This is even more critical during the rapid weight loss phase. Protein needs may increase and change based on health status, pregnancy, surgeries, healing, etc.
When it comes to fat, I do not recommend patients consuming excessive amounts of fat- At the same time I do not recommend patients go on a low fat diet. There is this misconception that since DS is causing fat and fat soluble vitamin malabsorption, then taking more fat (in excessive amounts) can solve the problem of vitamin deficiency. How about the possibility that some patients are causing their own vitamin deficiency by taking large volumes of fat which may results in more frequent bowel movements and decreased vitamin absorption.
It is not to be forgotten that each patient will respond differently with dietary changes after duodenal switch. Some patients may tolerate more and some less fat in their diet. After the initial 90 day post op phase I recommend that patients go slowly in adding new food items by giving it several days before adding another food item. i.e.; add carrots for 3-5 days to see how your body handles it before attempting to add another new item. The above is not the entire weight loss process or education and is only a small portion of the education needed before undergoing any WLS procedure. These recommendation are my recommendations for my patients with the Hess technique for Duodenal Switch.
Curved Adjustable Gastric Band Discontinued
May 19, 2016 11:19 am
The Curved Adjustable Gastric Band will be discontinued. Johnson and Johnson, the parent company of the Ethicon, is removing the Curved adjustable Gastric Band from its’ product line. This particular band is known as the Realize Band launched by Johnson & Johnson and did not gain much traction. The number of Adjustable gastric band placements have gone down significantly as the data have shown poor outcome over long term and a high complication and re-operative rates.

The following link is a copy of the letter from Ethicon Johnson and Johnson regarding the Curved Adjustable Gastric Bands Discontinuation: Realize Band removed from the Market.
Minimally Invasive Weight Loss Surgery
May 17, 2016 9:02 am
Minimally Invasive does not mean better, easier, proven outcomes or good excess weight loss. Weight loss surgical patients should be careful of catch phrases such as “less invasive”, “simpler”, “shorter recovery”, “outpatient” and many others that had been used to described procedures with less than optimal outcome. We should not forget the lessons learned from adjustable gastric banding which was also promoted as ” less invasive, simpler to perform, and be done as an outpatient with a short recovery “. We all know how that story has panned out. The overwhelming majority of patients who had an adjustable gastric banding have undergone revision, had it removed or had additional surgeries following the complications which were associated with this simple procedure.
When evaluating outcome data for weight loss surgical procedures, it is important to bear in mind that the long-term success of these procedures will take years to document. More often than not the early weight loss is significantly better than the long-term stable weight loss. This has been clearly documented in the case of the adjustable gastric banding and the gastric bypass and laparoscopic sleeve gastrectomy operation. Duodenal switch , as described by Dr. Hess using the percentage based technique, has the best long-term documented success of all of the weight loss surgical procedures. The scientific data reports 20+ years of successful excess weight loss with a Hess Duodenal Switch procedure. There has been an alternative proposed to Duodenal Switch recently, the SIPS and SADI procedures. As I have already stated in the past, these are not the same as the duodenal switch operation. Any suggestion or innuendos that SIPS/SADI is the same as the Duodenal Switch is deceptive and misleading. We have also seen attempts to use the same catch phrases as described above to promote these unproven procedures. The published data that’s been reported with SIPS/SADI is mostly short-term in small population studies. There are no long-term studies that have documented the efficacy of the SIPS/SADI procedure and “simpler” or minimally invasive does not mean better.
Magnesium Questions
May 11, 2016 6:07 am
Since our Webinar on Magnesium, I have received several Magnesium Questions recently regarding Magnesium deficiency. There is some evidence that calcium deficiency can not be corrected with an underlying magnesium deficiency. This may be due to the fact that magnesium is essential to converting Vitamin D to it’s active form and more information here. The active form of Vitamin D is needed to actively transport Calcium within the cell. This may be the confusion that calcium absorption needs magnesium. It is not needed directly but rather indirectly via Vitamin D.
Other cofactors needed in Vitamin D metabolism are:
Zinc (high doses antagonist with Magnesium and Copper)
Boron (raises Magnesium blood levels)
Vitamin K2
Vitamin A in small amounts
Further information regarding bone health and nutrients here.

Some important facts about Magnesium are:
- It is Absorbed in the distal Jejunum and Ileum (small intestines) and to some degree the colon.
- Plays an important role in Parathyroid Hormone synthesis which is also acted upon by Vitamin D
- Vitamin D increases Magnesium absorption
- All enzymes that metabolize Vitamin D require Magnesium
- Magnesium has a positive effect on Vitamin D deficiency.
- Magnesium and calcium are antagonist to each other on a cellular level (work against each other) They use an overlapping transport system for reabsorption within the kidneys and thereby compete with each other. Magnesium may also bind to calcium binding sites and intracellular protein binding sites due to their similarity.
- Calcium supplements can decrease Magnesium absorption.
- It Activates digestive enzymes for protein, fat and carbohydrate metabolism.
- Essential for protein synthesis
- Stores and moves energy acquired from digestion.
- Regulates Calcium via Vitamin D and increasing urinary excretion of calcium
Factors inhibiting Magnesium absorption:
- PPI
- Fiber
- Phytates
- Excessive unabsorbed fatty acids
- Calcium
- Phosphorus
- Protein

In summary, post Bariatric patients are at risk for magnesium deficiency and it plays an important role in overall health and bone health. Our practice recommends Magnesium Glycinate as the form for supplementation in at least a 2:1 ration with calcium. An example is: Calcium 2000mg daily to Magnesium Glycinate 1000mg daily. (Supplement based on your laboratory studies) We hope that this blog has answered some of your Magnesium Questions.
Does Your Sleeve Look Like this?
May 10, 2016 9:03 am
The re-shaping of the stomach for weight loss with a Sleeve Gastrectomy can be a technically challenging procedure. There are complications such as stricture, cork-screw stomach, GERD, nausea and vomiting that can lead to further health issues and possibly nutritional issues.
Upper GI pictures of Sleeved Stomach
In the following series of pictures you can visualize that the Sleeve Gastrectomy in the first picture is a hard angled S shape with two stricture points. The second picture points out the two stricture points and the outline the sleeve gastrectomy of a patient referred to our practice for complications of stricture and GERD post sleeve gastrectomy in need of revision. Surgical revision of gastric stricture is highly technical and challenging. It also takes experience in identifying possible options available to the patient.
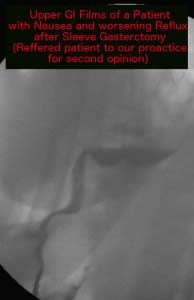

The outline in light blue depicts the shape a sleeve gastrectomy should follow.
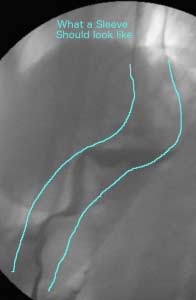
Why are strictures bad? What is the problem with having and living with a stricture? Strictures caused by Sleeve gastrectomy or Duodenal Switch, SIPS/SADI procedure can have detrimental effects. The long-term complications may include, irreversible injury to the esophagus and the stomach above the stricture, Teeth and gum damage, aspiration in addition to nutritional deficits because of the inability to tolerate healthy meals. Additional information regarding complications that can arise from stricture, nausea and vomiting here.
Strictures can not be repaired by dilation in most cases since on one side of the narrowed section is formed by the sample line. These should be addressed surgical by an experienced surgeon. Ideally a a stricture would be avoided at all cost by assuring that the sleeves are not done too tight and narrowed and that there are no sharp angles created when the stomach is divided during these procedures. The repair of these strictures of the stomach in the duodenal switch, sleeve and the SADI/SIPS procedures are complicated since the remnant stomach is removed and the options are limited. Additional information regarding stricture complications and pictures of other stricture types here.
Stricture after Sleeve Gastrectomy Duodenal Switch
May 01, 2016 9:45 pm
According to the American Society of Metabolic and Bariatric Surgery sleeve gastrectomy has become the most commonly performed operations in 2012. Sleeve gastrectomy became popular because of the high failure rate of the adjustable gastric banding and the issues with RNY pouch. The Sleeve Gastrectomy was performed many years prior to 2012 as a part of the Duodenal Switch procedure. Stricture is a complication occurring post Sleeve Gastrectomy and Duodenal Switch.
Stricture:
Sleeve gastrectomy may appear to be a simple procedure under the surface; however, it is fraught with very unique and challenging complications. These may include, but are not limited to, staple line failure resulting in leak, injury to the spleen, stricture, and even a rare and under diagnosed portal vein thrombosis. Technique is important in avoiding short and long-term complications. Strictures can be caused by making the sleeve stomach too narrow or by stapling in a fashion where the corkscrew stomach.
Some surgeons create a very narrow sleeved stomach in an attempt to maximize weight loss by increasing restriction. This can result in significant GERD in patient with no long-term benefit. Re-sleeving is another incidence were strictures can become an issue. These strictures are debilitating and almost all the time require surgical intervention. Balloon dilation by an endoscopy method is frequently unsuccessful. The patient who has a stricture should seek the attention of an experienced revision surgeon for surgical repair. Strictures are usually a short narrow segment of the stomach. The reason why sleeve gastrectomy strictures do not respond well to balloon dilatation is because of the staples line that is present on one side of the tube of the stomach that cannot be stretched.
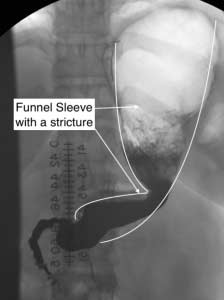
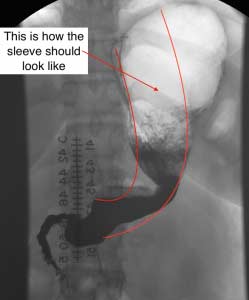
Some surgeons create a very narrow sleeved stomach in an attempt to maximize weight loss by increasing restriction. This can result in significant GERD in patient with no long-term benefit. Re-sleeving is another incidence were strictures can become an issue. These strictures are debilitating and almost all the time require surgical intervention. Balloon dilation by an endoscopy method is frequently unsuccessful. The patient who has a stricture should seek the attention of an experienced revision surgeon for surgical repair. Strictures are usually a short narrow segment of the stomach. The reason why sleeve gastrectomy strictures do not respond well to balloon dilatation is because of the staples line that is present on one side of the tube of the stomach that cannot be stretched.
An increasingly more complicated problem is when the stricture is caused by a spiraling of the staple line. This is quite frequently seen where the stapling of the stomach was started on the greater curvature of the stomach and rotated anteriorly causing a corkscrew effect of the stomach. A long segment stricture of the stomach cannot be corrected by balloon angioplasty and would require surgical intervention.
I have been involved with numerous repairs of strictures on sleeve gastrectomies and Duodenal Switch stomach from other institutions. In my opinion, repeated endoscopy and balloon dilatation only complicate further care by compromising the tenuous tissue of a strictured stomach due to scaring and blood supply. As above-stated earlier it is critical that a patient who is experiencing significant reflux, changes in nausea and vomiting, suspected stricture or narrowing, or has a corkscrew stomach to be seen by an experienced surgeon for surgical repair. See the following Blog for health issues that can occur or progress with strictures.
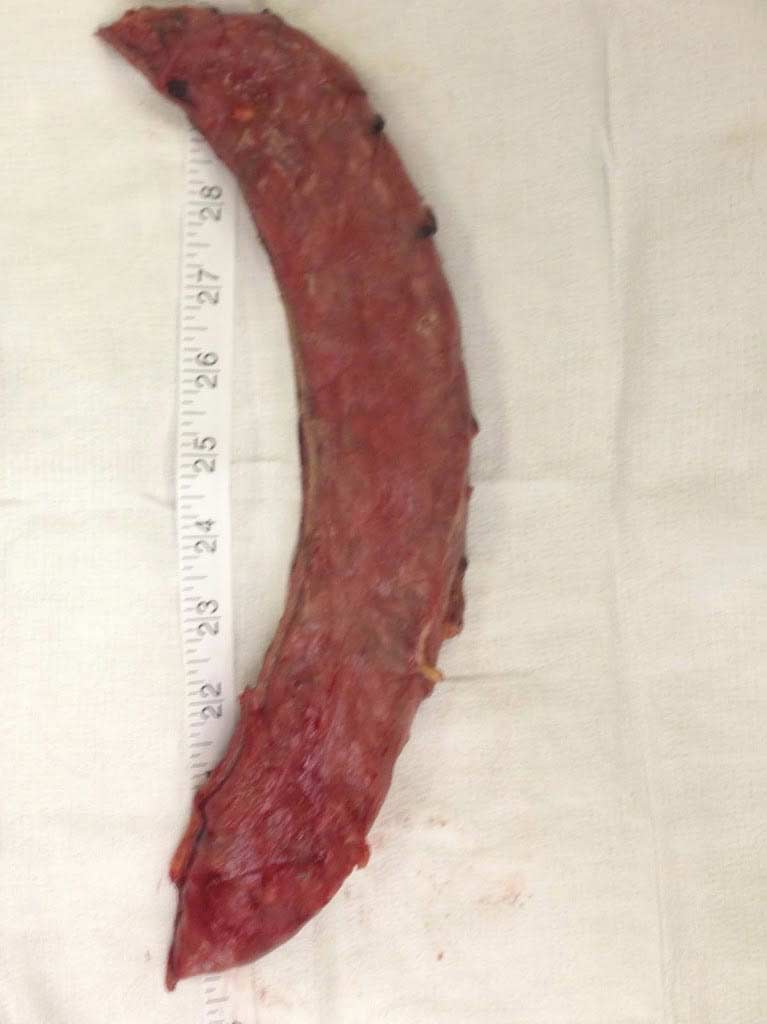
Sleeve Gastrectomy specimen picture.
The Citric Acid Cycle- AnimatedExclusive Member Content
April 26, 2016 11:54 am
Vitamin D2 Vs D3
March 24, 2016 9:17 am
Thank you to Contributor: Mariam Michelle Gyulnazaryan
Vitamins are organic, essential nutrients that are necessary to keep your body in good health. Most vitamins must be obtained through diet because they cannot be synthesized in the body. However, the human body is able to make its own vitamin D in the skin through sun exposure or it can be obtained by food and supplements of Vitamin D3.
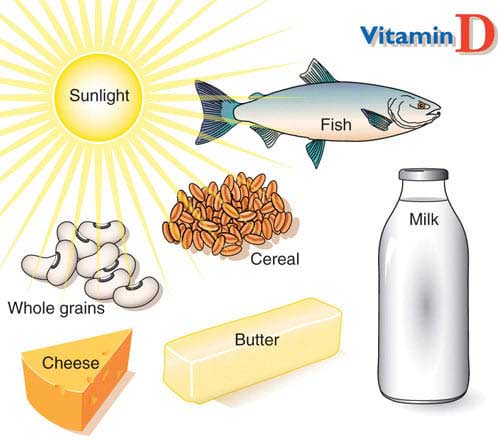
Vitamin D is a fat-soluble vitamin that is responsible for regulating muscle contraction, immune function, bone health, and intestinal absorption of magnesium, calcium, phosphate, iron, and zinc. Good sources of Vitamin D include sun exposure, dairy products, fatty fish, fortified orange juice, cod liver oil, mushrooms, and supplements.
There are two types of Vitamin D: D2 (ergocalciferol) and D3 (cholecalciferol). Both types have the same mechanism of action, but different sources and kinetics.
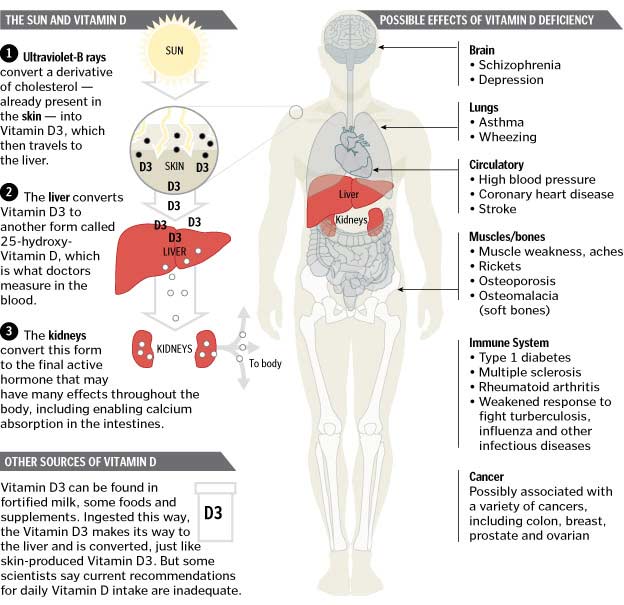
Ergocalciferol is easily obtained through Vitamin D-rich foods in normal anatomy. However, a post Duodenal Switch patient will have less absorption of Vitamin D via food due to fat malabsorption. Ergocalciferol is hydroxylated to ercalcidiol [25(OH)D2] in the liver. Its second hydroxylation takes places in the kidney, where it is converted to the active form of Vitamin D2 known as ercalcitriol [1,25(OH)2D2]. Now in it’s active form, Vitamin D2 can bind to the Vitamin D receptor (VDR) and help the body where it’s needed.
In the epidermis of the skin, precursor 7-dehydrocholesterol (7-DHC) forms cholecalciferol as a result of UVB radiation. Several factors such as increased skin pigmentation, age, and sunscreen application reduce the skin’s production of choleciferol (6). Cholecalciferol is hydroxylated in the liver to become calcidiol [25(OH)D3]. It is then moved to the kidney for further hydroxylation to Vitamin D3’s active form known as calcitriol [1,25(OH)2D3], also called calcifediol. The active form allows binding to VDR for biological activity.
Both forms of Vitamin D have been shown to effectively increase 25(OH)D levels. Research shows that after administering a single dose of 50,000 international units (IU) Vitamin D2 or D3, both experienced a similar increase in serum 25(OH)D concentration. However, Vitamin D2 levels rapidly declined while Vitamin D3 levels remained high (1). Further studies have confirmed that Vitamin D3 is more effective in elevating and maintaining 25(OH)D levels for a longer amount of time (5). Scientists believe the most reasonable explanation for Vitamin D3’s substantial efficacy is its higher affinity to metabolites, which results in a longer circulating half-life than Vitamin D2 making it more potent(4). For a post Duodenal Switch patient, due to fat malabsorption, it is important to use “Dry” Water Miscible form of Vitamin D3.

A 25-hydroxy Vitamin D blood test is the most accurate way to measure levels. A level between 20 ng/mL-50 ng/mL may be considered sufficient, however in our bariatric practice we would like to keep the levels in 60-80 ng/mL. It is worth nothing that recently the reference ranges was increase to 30-100 ng/mL. Treatments of Vitamin D deficiency include frequent sun exposure, fortified foods, supplements, and injectables. in addition to 50000IU of vitamin D on daily basis in emulsified (water soluble) formulary or unto 600,000IU in injection form. The parallel guide for adequate vitamin D supplementation is normalization of PTH levels. Monitoring these levels is imperative in a post bariatric patient.
In conclusion, studies have shown that Vitamin D2 and D3 are not interchangeable. Although they have comparable absorption, Vitamin D2 has a shorter duration of action which makes it less potent than Vitamin D3. Researchers have shown that neither form is harmful to treat Vitamin D deficiency, but they should not be considered bio-equivalent.
References
1. Armas LAG, Hollis BW, Heaney RP. Vitamin D2 is much less effective than Vitamin D3 in humans. Journal of Clinical Endocrinology & Metabolism. 2004; 89(11) 5387-5391.
2. Creighton D, Ignaszewski A, Francis G. Vitamin D: new d-fence against cardiovascular disease. BCMJ. 2012; 54(3) 136-140.
3. Holick MF, Schnoes HK, DeLuca HF. Identification of 1,25-Dihydroxycholecalciferol, a form of Vitamin D3 metabolically active in the intestine. PNAS. 1971; 68(4) 803-804.
4. Hollis BW. Comparison of equilibrium and disequilibrium assay conditions for ergocalciferol, cholecalciferol and their major metabolites. J Steroid Biochem. 1984; 21(1) 81-86.
5. Houghton LA, Vieth R. The case against ergocalciferol (Vitamin D2) as a vitamin supplement. Am J Clin Nutr. 2006; 84 (4): 694-697.
6. Howick Mf, Binkley NC, Bischoff-Ferrari HA, Gordon CM, Hanley DA, Heaney RP, Murad MH, Weaver CM. Evaluation, treatment and prevention of Vitamin D deficiency: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. 2011; 96(7) 1911-1930.
7. Johal M, Levin A. Vitamin D and Parathyroid Hormone in general populations: understandings in 2009 and applications to chronic kidney disease. CJASN. 2009; 4(9) 1508-1514.
8. Tetley EA, Brule D, Cheney MC, Davis Cd, Esslingen KA, Fischer PWF, Friedl KE, Green-Finestone LA, Guenther PM, Klurfeld DM, L’Abbe MR, McMurry KY, Starke-Reed PE, Trumbo PR. Dietary reference intakes for Vitamin D: justification for a review of the 1997 values. Am J Clin Nutr. 2009; 89(3) 719-727.
9. Tripkovic L, Lambert H, Hard K, Smith CP, Bucca G, Penson S, Chope G, Hypponen E, Berry J, Vieth R, Lanham-New S. Comparison of Vitamin D2 and Vitamin D3 supplementation in raising serum 25-hydroxyvitamin D status: a systematic review and meta-analysis. Am J Clin Nutr. 2012; 95(6) 1357-1364.
Enhanced Cognitive Function after Bariatric Surgery
March 18, 2016 6:51 am
The adverse effects of obesity reduce the body’s natural potential of optimal physical, mental health and cognitive function. Obesity is associated with a greater risk of health problems such as hypertension, stroke, diabetes, and sleep apnea. These issues attribute to an increased risk of dementia and cognitive dysfunction.
Glucose homeostasis plays a key role in the neural mechanisms of the brain. Insulin signals nutrients by circulating within the body in proportion to body fat mass. In addition to other regulatory mechanisms, this allows the brain to control feeding behavior by stimulating energy storage and metabolic homeostasis. Metabolic imbalances modify insulin sensitivity and lead to impaired glucose output inhibition [Qatanani and Lazar et al., 2007 (1)].

Free radicals are formed when weak molecular bonds are split. Their instability causes them to attack neighboring stable molecules and lead to a chain reaction of disturbing living cells. Antioxidants, such as vitamins C and E, defend the body from the damaging effects of free radicals by acting like scavengers. They protect cells from tissue damage that can potentially lead to disease.
Moreover, insulin resistance links oxidative stress, which is the continuous imbalance between free radical production and the body’s antioxidant defenses to detoxify its harmful effects. Enhanced oxidative stress is a result of accumulated fat, which impairs the secretion of insulin and damages glucose uptake in muscle and fat. Increased oxidative stress is the underlying cause of pathogenesis in vascular cell walls that lead to the development of cardiovascular problems, plaque formation. Data suggests, in a study conducted by Dr. Convit (2) in 2002, that management of blood sugar levels may enhance memory and possibly decrease the risk of Alzheimer’s disease.
In congruence with these findings, added stress due to excess weight can negatively affect the anatomy and physiology of the body. A study in 2010, led by Dr. Thompson (3), concluded that obesity is associated with “atrophy in brain areas targeted by neurodegeneration: hippocampus, frontal lobes, and thalamus” [Raji et al., 2010 (3)]. These brain regions play a critical role in the maintenance of memory, executive function, and sensory interpretation, respectively.
Central respiratory function is also disrupted by the mechanical effects of obesity. Reduced lung expansion is especially destructive during sleep. Obstructive sleep apnea is a disorder where breathing stops for brief periods because of an obstructed upper airway. Excess weight and increasing body mass index (BMI) restricts expansion of the chest wall and increases airway resistance, which decreases lung volume [Zammit et al. 2010 (4)]. This boosts respiratory muscle workload for consistent breathing. Complications of sleep apnea include fatigue, heart problems, metabolic syndrome, and more.
Cognitive impairments lead to deficits in executive function, response, reflex time, planning, and memory [Spitznagel et al. 2013 (5)]. Blood sugar levels, oxidative state, respiration and other mechanisms influence our cognitive abilities. Weight loss from bariatric surgery may reduce the comorbidities of an obese patient. The primary outcomes are improvements with diabetes, blood pressure, glucose levels, sleep apnea, BMI, and excess weight resolutions.

Weight loss surgery reverses the stressors of the body to permit the development and preservation of cognitive function. By improving anatomical aspects of physical health, the overall mental well-being of patients is remarkably enhanced.
A number of studies have looked at the short [Gunstad 2011(6)] and intermediate [Alosco 2013, (7)] term improvement in memory function after weight loss surgery
Thank you to Contributor: Mariam Michelle Gyulnazaryan
References for Cognitive Function
- Qatanani M, Lazar MA. Mechanisms of obesity-associated insulin resistance. Genes & Dev. 2007; 21: 1443-1455.
- Convit A, Wolf OT, Tarshish C, de Leon MJ. Reduced glucose tolerance is associated with poor memory performance and hippocampal atrophy among normal elderly. PNAS. 2013; 100 (4): 2019-2022.
- Raji CA, Ho AJ, Parikshak N, Becker JT, Lopez OL, Kuller LH, Hua X, Leow AD, Toga AW, Thompson PM. Brain structure and obesity. Hum Brain Mapp. 2010; 31(3): 353-364.
- Zammit C, Liddicoat H, Moonsie I, Makker H. Obesity and respiratory diseases. Int J Gen Med. 2010; 3:335-343.
- Spitznagel MG, Alosco M, Strain G, Devlin M, Cohen R, Paul R, Crosby RD, Mitchell JE, Gunstad J., Cognitive function predicts 24-month weight loss success following bariatric surgery. Surg Obes Relat Dis. 2013; 9(5): 765-770.
- John Gunstad, Gladys Strain, Michael J. Devlin, Rena Wing, Ronald A. Cohen, Robert H. Paul, Ross D. Crosby, James E. Mitchell, 2011, ‘Improved memory function 12 weeks after bariatric surgery’, Surgery for Obesity and Related Diseases, vol. 7, no. 4, pp. 465-472
- Michael L. Alosco, Mary Beth Spitznagel, Gladys Strain, Michael Devlin, Ronald Cohen, Robert Paul, Ross D. Crosby, James E. Mitchell, John Gunstad, 2013, ‘Improved memory function two years after bariatric surgery’, Obesity, vol. 22, no. 1, pp. 32-38
- Furukawa S, Fujita T, Shimabukuro M, Iwaki M, Yamada Y, Nakajima Y, Nakayama O, Makishima M, Matsuda M, Shimomura I. Increased oxidative stress in obesity and its impact on metabolic syndrome. J Clin Invest. 2004; 114(12): 1752-1761.
- Mitchell JE, de Zwaan M. Psychosocial assessment and treatment of bariatric surgery patients. 2011;6: 103-109.
- Nguyen JCD, Killcross AS, Jenkins TA. Obesity and cognitive decline: role of inflammation and vascular changes. Front Neurosci. 2014; 8: 375.
- Chan JSY, Yan JH, Payne VG. The impact of obesity and exercise on cognitive aging. Front Aging Neurosci. 2013; 5: 97.
Shared Success Story – Albert L.
March 07, 2016 10:46 am
Lose weight, eat smaller portions, eat healthy, go to the gym, don’t eat bread, don’t eat starches, try this diet try that diet….. on and on.
It is so easy for dietitians, nutritionists, cardiologists, family members to speak these words. Being the one with the weight issue, it would drive me crazy hearing all the smart advice everyone had for me. I tried it all without success! Some for one day, some for longer, the results were always the same. I would lose a few pounds and in the end I would gain more. I imagine that the advice givers really didn’t understand the fatigue and appetite that comes with the extra pounds. At 39 years old, 245lbs, on blood pressure and cholesterol meds, all I could see was a life of diabetes and heart disease. Oh, the days I spent in department stores looking at designer clothes I couldn’t wear, talking to women who wouldn’t see past my belly, being the guy at the pool with his shirt on and most of all facing a very rocky future.


The day I walked into Dr Keshishian’s office was the day my life changed. He looked me in the eyes and told me it’s all going to be better. I had my surgery in June and my recovery was unusually fast. The pounds were dropping daily and within 6 weeks my cardiologist took me off my blood pressure and cholesterol medications. At eight months after surgery, I am so close to my goal of 180lbs. I have to admit that I would have reached my goal months ago. But a trip to Australia, wining and dining my new fiancé put me off track. But I’m happy to say I’m well on my way to success. Because I am feeling so much healthier, I have joined a gym. Since surgery, I don’t have a huge appetite so I am eating smaller and healthier portions. The future is looking very very bright. Thank you Doc.”
-Albert L.