
Category: Uncategorized
Shared Success Story- Heidi
June 02, 2016 7:59 am
My name is Heidi and this is my weight loss journey. I had been struggling with my weight for years and was actively researching different surgical procedures available. I was also trying everything to lose the weight on my own. My wake up call to take action was one night when my husband said, “I’m worried about you and want you around for a long time.” I knew I had to do something. If someone loved me that much I needed to love myself enough to change.


So the very next day I made an appointment with my Primary Care Physician who recommended Dr. Ara Keshishian. That afternoon I called Dr. Keshishian’ office, scheduled a consultation and began what was about to be one of the greatest journeys of my life. I was approved within a month and ready to go.
In 2012, I had my Duodenal Switch with the great Dr. Keshishian. I was hopeful post op and determined to succeed. I knew with my husband’s and family’s love and support I could do it. I wanted to lose the weight for me, my husband and our future children so they had the healthy, happy mom they deserved. My Surgery weight was 220 ( Started at 230) I reached my goal at 10 months post op at 125lbs. Since having my DS I have had 1 (almost 2) amazing son’s. Duodenal Switch made this possible. I have my older son and I am currently 8 months pregnant with my 2nd son. Duodenal Switch did not just allow me to lose the weight that kept me from living life but it allowed me to get healthy and live life to the fullest. I am grateful everyday for my DS, my amazing husband, my boys, and Dr. Keshishian.
I am simply blessed. Would I do it again? In a heart beat.
Starting weight- 230
Surgery weight- 220
Goal Weight- 125
Current-130
Probiotics and Prebiotics
May 26, 2016 1:59 pm
Probiotics and Prebiotics are an important part of our overall general and gastrointestinal health. The gastrointestinal (GI) tract is a large, muscular tube that allows the digestion of food. The intestinal lining of the tract plays a role in absorbing vital nutrients and acts as a barrier for the macromolecules and microorganism from circulation. Our GI system is exposed to many bacterial agents that undergo fermentation in the mucosa. The type of fermentation carried out in the gut is greatly influenced by the types of bacteria found in the lumen.
The GI microflora is an elaborate ecosystem consisting of neutral and beneficial bacteria whose balance impacts overall health. This microenvironment consists of about 400 different bacterial species that make up approximately 100 billion organisms in the gut. The flora functions in nutrient consumption, vitamin production, detoxification, hormone activity, and other regulatory processes. Abnormal microbial balance or colonization results in dysbiosis, where the deviant nature of bacteria may become pathological (7). Dysbiosis is a contributing factor to many degenerative and chronic diseases.

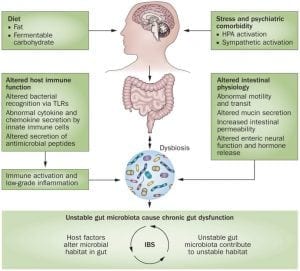
Benefits of Probiotics and Prebiotics:
Our bodies are full of both good and bad bacteria. Probiotics contain live bacteria and yeasts, whose activity is beneficial when present in appropriate amounts (11,12). These helpful microorganisms regulate the body’s systems in several ways:
- Gastrointestinal: Probiotics work to reduce infectious diarrhea, specifically types identified by antibiotic use (1). Certain strains enhance stool consistency and bowel movement frequency. Probiotics have also proven effective in alleviating bloating and gas found in irritable bowel syndrome (9). Further studies suggest that specialized strains aid in milder forms of ulcerative colitis, an inflammatory bowel disease. A recent Russian study suggested eradication of SIBO and IBS using a combination of Bifidobacterium bifidum, Bifidobacterium longum, Bifidobacterium infantis and Lactobacillus rhamnosus, called Florasan-D available in Russia. These findings were presented at the 2015 Gut Microbiota for Health World Summit in Barcelona, Spain by Elena Polouektova, MD, a researcher at I.M. Sechenov First Moscow State Medical University.
- Weight Loss: A clinical study (8) revealed reduced body fat in patients who consumed yogurt (probiotic source), although there were no observed changes in weight. Another study, published in the 2011 European Journal of Clinical Nutrition (6), found that subjects who consumed fermented milk that contained a specific bacterial strain observed abdominal fat and weight loss, when compared to subjects drinking a control.
- Immunity: Although the clinical implications of this evidence are still being studied, it has been found that immune response strength is greatly improved through certain strains of probiotics (2,4). They have also been shown to lighten hypersensitivity reactions and normalize added mucosal dysfunction.
- Other Uses: Bacteria also reside in the mouth. Probiotics play an essential role in oral health, where they reduce throat infection, bad breath and periodontal disease, a gum infection (5). There have been claims that probiotics lower the effects of some skin conditions, prevent colon cancer, lower blood pressure and cholesterol, and alleviate anxiety and depression (3). Future studies are working towards the consistency of these claims.
Probiotics regulate the movement of food through the digestive system. They help replace unwanted bacteria and maintain the mucosal microenvironment to avoid dysfunction. Prebiotics are fiber compounds that move through the GI tract undigested. Prebiotics are important in stimulating probiotic growth and maintaining a stable environment for their optimal activity (13). The best way to get all the powerful benefits of probiotics is through consuming foods that are prepared by bacterial fermentation. Supplements are also available. Previous blog regarding probiotic supplements here. Previous blog regarding probiotics, C.Diff and Hyperoxaluria here.
Written by: Mariam Michelle Gyulnazaryan & Dr. Ara Keshishian
References
- Bowen, J. M., Stringer, A. M., Gibson, R. J., Yeoh, A. S., Hannam, S., & Keefe, D. M. (2007). VSL# 3 probiotic treatment reduces chemotherapy-induced diarrhoea and weight loss. Cancer biology & therapy, 6(9), 1445-1450.
- Chiang, B. L., Sheih, Y. H., Wang, L. H., Liao, C. K., & Gill, H. S. (2000). Enhancing immunity by dietary consumption of a probiotic lactic acid bacterium (Bifidobacterium lactis HN019): optimization and definition of cellular immune responses. European journal of clinical nutrition, 54(11), 849-855.
- Foster, J. A., & Neufeld, K. A. M. (2013). Gut–brain axis: how the microbiome influences anxiety and depression. Trends in neurosciences, 36(5), 305-312.
- Isolauri, E., Sütas, Y., Kankaanpää, P., Arvilommi, H., & Salminen, S. (2001). Probiotics: effects on immunity. The American journal of clinical nutrition, 73(2), 444s-450s.
- Krasse, P., Carlsson, B., Dahl, C., Paulsson, A., Nilsson, A., & Sinkiewicz, G. (2005). Decreased gum bleeding and reduced gingivitis by the probiotic Lactobacillus reuteri. Swedish dental journal, 30(2), 55-60.
- Merenstein, D., Murphy, M., Fokar, A., Hernandez, R. K., Park, H., Nsouli, H., … & Shara, N. M. (2010). Use of a fermented dairy probiotic drink containing Lactobacillus casei (DN-114 001) to decrease the rate of illness in kids: the DRINK study A patient-oriented, double-blind, cluster-randomized, placebo-controlled, clinical trial. European journal of clinical nutrition, 64(7), 669-677.
- Myers, S. P. (2004). The causes of intestinal dysbiosis: a review. Altern Med Rev, 9(2), 180-197.
- Omar, J. M., Chan, Y. M., Jones, M. L., Prakash, S., & Jones, P. J. (2013). Lactobacillus fermentum and Lactobacillus amylovorus as probiotics alter body adiposity and gut microflora in healthy persons. Journal of functional foods, 5(1), 116-123.
- Prantera, C., & Scribano, M. L. (2009). Antibiotics and probiotics in inflammatory bowel disease: why, when, and how. Current opinion in gastroenterology, 25(4), 329-333.
- Reid, G., Jass, J., Sebulsky, M. T., & McCormick, J. K. (2003). Potential uses of probiotics in clinical practice. CLINICAL microbiology Reviews, 16(4), 658-672.
- Rolfe, R. D. (2000). The role of probiotic cultures in the control of gastrointestinal health. The Journal of nutrition, 130(2), 396S-402S.
- Sanders, M. E. (2008). Probiotics: definition, sources, selection, and uses. Clinical Infectious Diseases, 46(Supplement 2), S58-S61.
- Schrezenmeir, J., & de Vrese, M. (2001). Probiotics, prebiotics, and synbiotics—approaching a definition. The American journal of clinical nutrition, 73(2), 361s-364s.
Weight loss Surgery for Treatment of Diabetes
May 25, 2016 7:21 am
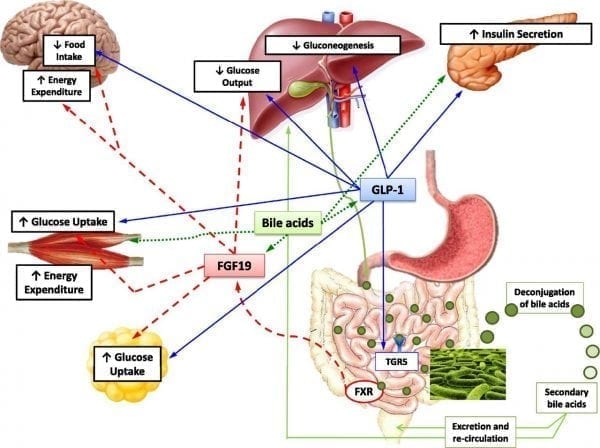
New guidelines and recommendation are coming out of the second Diabetes Surgery Summit in the Fall of 2015. One major change is Metabolic or Weight Loss Surgery for the treatment of Diabetes. With all the advances made in newer classes of medication for treatment of diabetes, the majority of patients who are being treated fail to get to achieve the desired results of lowered blood glucose level. This is in contrast where weight loss surgical procedures such as Duodenal Switch can results in >95% cure rate of type II diabetes.
The American Diabetes Association has made the recommendation for weight loss surgical procedures be considered as a treatment option for type II diabetes.
Summarizing their criteria “According to the new Guidelines, metabolic surgery should be recommended to treat type 2 diabetes in patients with Class III obesity (BMI greater than or equal to 40 kg/m2), as well as in those with Class II obesity (BMI between 35 and 39.9 kg/m2) when hyperglycemia is inadequately controlled by lifestyle and medical therapy. It should also be considered for patients with type 2 diabetes who have a BMI between 30 and 34.9 kg/m2 if hyperglycemia is inadequately controlled, the authors agreed. The Consensus S
tatement also recognizes that BMI thresholds in Asian patients, who develop type 2 diabetes at lower BMI than other populations, should be lowered 2.5 kg/m2 for each of these categories. ”
This is a remarkable change in thought and policy on diabetic treatment and long term strategies that can only improve patient outcomes. Stabilization and blood glucose hemostasis can only improve patient health, health care utilization and health care costs.
Inadequate Weight loss and Weight Regain
May 24, 2016 7:56 am
There were numerous causes for the inadequate weight loss and or weight regain after weight loss surgery.
These factors may include:
1-Type of the surgery: Duodenal Switch, RNY, Adjustable Gastric Banding, Intragastric Balloon, etc.
2-Patients metabolic state (age, activity level, hormones state etc)
3-Co-morbidities
4-Patient compliance
5-Other
Each and every one of these may be an independent factor or may be a contributing cause.
In our experience, patients non-compliance is not as common as others believe. Frequently, we see patients in our office where they have been told that the poor outcome of the surgery is “their fault”
We see this with RNY, and Band patients as well as some of the duodenal switch patients who are seeking advice for weight regain or inadequate weight loss.
I would like to talk about the issues of inadequate weight loss or regain post Duodenal Switch specifically. Duodenal switch operation as described by Dr. Hess, outlined the division of the small bowel lengths to be proportional to each and every patients own total bowel lengths. This meant that two patients with the same BMI and weight will end up with two different lengths for common and alimentary limbs if there total length of the bowel is different. Unfortunately, too often patients are given a “standard” or “set” ( not clear what that word means, since there is no established standard in the literature) length for common channels and alimentary channels regardless of the total small bowel length. In some patients, those lengths may result in acceptable weight loss. However, quite frequently a patient with a preselected length for the common and alimentary limbs will end up either loosing too much weight and have nutritional problems or not loose adequate weight. As with all practices, we have over the years had patients who have had nutritional deficiencies and excessive weight loss or have had inadequate weight loss. Looking at the raw numbers however, we have had more patient from other practices that have come to us for revisions and corrections of lengths of the bowel lengths from other practices that our own patients have required.
Another level of the confusion is the improper interchanging of the “SIPS and SADI” procedures with the duodenal switch operation. As I have said in the past repeatedly, SIPS and SAID are not the same as the duodenal switch- and attempt to call these different procedures the same is misleading to say the least.
The other category of weight regain or inadequate weight loss includes medications and new health issues. Discussed in a previous blog, there are many medications that can influence weight gain. It is important to work with your health care provider to find medications that have a positive effect on symptoms without added side effects whenever possible.
In summary, weight re-gain or inadequate weight loss can have many facets. However, surgical technique can provide an advantage. Each aspect should be addressed and identified.
Curved Adjustable Gastric Band Discontinued
May 19, 2016 11:19 am
The Curved Adjustable Gastric Band will be discontinued. Johnson and Johnson, the parent company of the Ethicon, is removing the Curved adjustable Gastric Band from its’ product line. This particular band is known as the Realize Band launched by Johnson & Johnson and did not gain much traction. The number of Adjustable gastric band placements have gone down significantly as the data have shown poor outcome over long term and a high complication and re-operative rates.

The following link is a copy of the letter from Ethicon Johnson and Johnson regarding the Curved Adjustable Gastric Bands Discontinuation: Realize Band removed from the Market.
Minimally Invasive Weight Loss Surgery
May 17, 2016 9:02 am
Minimally Invasive does not mean better, easier, proven outcomes or good excess weight loss. Weight loss surgical patients should be careful of catch phrases such as “less invasive”, “simpler”, “shorter recovery”, “outpatient” and many others that had been used to described procedures with less than optimal outcome. We should not forget the lessons learned from adjustable gastric banding which was also promoted as ” less invasive, simpler to perform, and be done as an outpatient with a short recovery “. We all know how that story has panned out. The overwhelming majority of patients who had an adjustable gastric banding have undergone revision, had it removed or had additional surgeries following the complications which were associated with this simple procedure.
When evaluating outcome data for weight loss surgical procedures, it is important to bear in mind that the long-term success of these procedures will take years to document. More often than not the early weight loss is significantly better than the long-term stable weight loss. This has been clearly documented in the case of the adjustable gastric banding and the gastric bypass and laparoscopic sleeve gastrectomy operation. Duodenal switch , as described by Dr. Hess using the percentage based technique, has the best long-term documented success of all of the weight loss surgical procedures. The scientific data reports 20+ years of successful excess weight loss with a Hess Duodenal Switch procedure. There has been an alternative proposed to Duodenal Switch recently, the SIPS and SADI procedures. As I have already stated in the past, these are not the same as the duodenal switch operation. Any suggestion or innuendos that SIPS/SADI is the same as the Duodenal Switch is deceptive and misleading. We have also seen attempts to use the same catch phrases as described above to promote these unproven procedures. The published data that’s been reported with SIPS/SADI is mostly short-term in small population studies. There are no long-term studies that have documented the efficacy of the SIPS/SADI procedure and “simpler” or minimally invasive does not mean better.
Magnesium Questions
May 11, 2016 6:07 am
Since our Webinar on Magnesium, I have received several Magnesium Questions recently regarding Magnesium deficiency. There is some evidence that calcium deficiency can not be corrected with an underlying magnesium deficiency. This may be due to the fact that magnesium is essential to converting Vitamin D to it’s active form and more information here. The active form of Vitamin D is needed to actively transport Calcium within the cell. This may be the confusion that calcium absorption needs magnesium. It is not needed directly but rather indirectly via Vitamin D.
Other cofactors needed in Vitamin D metabolism are:
Zinc (high doses antagonist with Magnesium and Copper)
Boron (raises Magnesium blood levels)
Vitamin K2
Vitamin A in small amounts
Further information regarding bone health and nutrients here.

Some important facts about Magnesium are:
- It is Absorbed in the distal Jejunum and Ileum (small intestines) and to some degree the colon.
- Plays an important role in Parathyroid Hormone synthesis which is also acted upon by Vitamin D
- Vitamin D increases Magnesium absorption
- All enzymes that metabolize Vitamin D require Magnesium
- Magnesium has a positive effect on Vitamin D deficiency.
- Magnesium and calcium are antagonist to each other on a cellular level (work against each other) They use an overlapping transport system for reabsorption within the kidneys and thereby compete with each other. Magnesium may also bind to calcium binding sites and intracellular protein binding sites due to their similarity.
- Calcium supplements can decrease Magnesium absorption.
- It Activates digestive enzymes for protein, fat and carbohydrate metabolism.
- Essential for protein synthesis
- Stores and moves energy acquired from digestion.
- Regulates Calcium via Vitamin D and increasing urinary excretion of calcium
Factors inhibiting Magnesium absorption:
- PPI
- Fiber
- Phytates
- Excessive unabsorbed fatty acids
- Calcium
- Phosphorus
- Protein

In summary, post Bariatric patients are at risk for magnesium deficiency and it plays an important role in overall health and bone health. Our practice recommends Magnesium Glycinate as the form for supplementation in at least a 2:1 ration with calcium. An example is: Calcium 2000mg daily to Magnesium Glycinate 1000mg daily. (Supplement based on your laboratory studies) We hope that this blog has answered some of your Magnesium Questions.
Does Your Sleeve Look Like this?
May 10, 2016 9:03 am
The re-shaping of the stomach for weight loss with a Sleeve Gastrectomy can be a technically challenging procedure. There are complications such as stricture, cork-screw stomach, GERD, nausea and vomiting that can lead to further health issues and possibly nutritional issues.
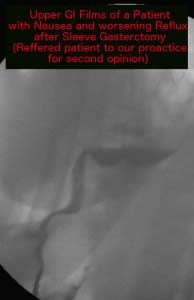
Upper GI pictures of Sleeved Stomach
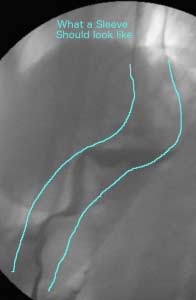
In the following series of pictures you can visualize that the Sleeve Gastrectomy in the first picture is a hard angled S shape with two stricture points. The second picture points out the two stricture points and the outline the sleeve gastrectomy of a patient referred to our practice for complications of stricture and GERD post sleeve gastrectomy in need of revision. Surgical revision of gastric stricture is highly technical and challenging. It also takes experience in identifying possible options available to the patient.

The outline in light blue depicts the shape a sleeve gastrectomy should follow.
Why are strictures bad? What is the problem with having and living with a stricture? Strictures caused by Sleeve gastrectomy or Duodenal Switch, SIPS/SADI procedure can have detrimental effects. The long-term complications may include, irreversible injury to the esophagus and the stomach above the stricture, Teeth and gum damage, aspiration in addition to nutritional deficits because of the inability to tolerate healthy meals. Additional information regarding complications that can arise from stricture, nausea and vomiting here.
Strictures can not be repaired by dilation in most cases since on one side of the narrowed section is formed by the sample line. These should be addressed surgical by an experienced surgeon. Ideally a a stricture would be avoided at all cost by assuring that the sleeves are not done too tight and narrowed and that there are no sharp angles created when the stomach is divided during these procedures. The repair of these strictures of the stomach in the duodenal switch, sleeve and the SADI/SIPS procedures are complicated since the remnant stomach is removed and the options are limited. Additional information regarding stricture complications and pictures of other stricture types here.
Enhanced Cognitive Function after Bariatric Surgery
March 18, 2016 6:51 am
The adverse effects of obesity reduce the body’s natural potential of optimal physical, mental health and cognitive function. Obesity is associated with a greater risk of health problems such as hypertension, stroke, diabetes, and sleep apnea. These issues attribute to an increased risk of dementia and cognitive dysfunction.
Glucose homeostasis plays a key role in the neural mechanisms of the brain. Insulin signals nutrients by circulating within the body in proportion to body fat mass. In addition to other regulatory mechanisms, this allows the brain to control feeding behavior by stimulating energy storage and metabolic homeostasis. Metabolic imbalances modify insulin sensitivity and lead to impaired glucose output inhibition [Qatanani and Lazar et al., 2007 (1)].

Free radicals are formed when weak molecular bonds are split. Their instability causes them to attack neighboring stable molecules and lead to a chain reaction of disturbing living cells. Antioxidants, such as vitamins C and E, defend the body from the damaging effects of free radicals by acting like scavengers. They protect cells from tissue damage that can potentially lead to disease.
Moreover, insulin resistance links oxidative stress, which is the continuous imbalance between free radical production and the body’s antioxidant defenses to detoxify its harmful effects. Enhanced oxidative stress is a result of accumulated fat, which impairs the secretion of insulin and damages glucose uptake in muscle and fat. Increased oxidative stress is the underlying cause of pathogenesis in vascular cell walls that lead to the development of cardiovascular problems, plaque formation. Data suggests, in a study conducted by Dr. Convit (2) in 2002, that management of blood sugar levels may enhance memory and possibly decrease the risk of Alzheimer’s disease.
In congruence with these findings, added stress due to excess weight can negatively affect the anatomy and physiology of the body. A study in 2010, led by Dr. Thompson (3), concluded that obesity is associated with “atrophy in brain areas targeted by neurodegeneration: hippocampus, frontal lobes, and thalamus” [Raji et al., 2010 (3)]. These brain regions play a critical role in the maintenance of memory, executive function, and sensory interpretation, respectively.
Central respiratory function is also disrupted by the mechanical effects of obesity. Reduced lung expansion is especially destructive during sleep. Obstructive sleep apnea is a disorder where breathing stops for brief periods because of an obstructed upper airway. Excess weight and increasing body mass index (BMI) restricts expansion of the chest wall and increases airway resistance, which decreases lung volume [Zammit et al. 2010 (4)]. This boosts respiratory muscle workload for consistent breathing. Complications of sleep apnea include fatigue, heart problems, metabolic syndrome, and more.
Cognitive impairments lead to deficits in executive function, response, reflex time, planning, and memory [Spitznagel et al. 2013 (5)]. Blood sugar levels, oxidative state, respiration and other mechanisms influence our cognitive abilities. Weight loss from bariatric surgery may reduce the comorbidities of an obese patient. The primary outcomes are improvements with diabetes, blood pressure, glucose levels, sleep apnea, BMI, and excess weight resolutions.

Weight loss surgery reverses the stressors of the body to permit the development and preservation of cognitive function. By improving anatomical aspects of physical health, the overall mental well-being of patients is remarkably enhanced.
A number of studies have looked at the short [Gunstad 2011(6)] and intermediate [Alosco 2013, (7)] term improvement in memory function after weight loss surgery
Thank you to Contributor: Mariam Michelle Gyulnazaryan
References for Cognitive Function
- Qatanani M, Lazar MA. Mechanisms of obesity-associated insulin resistance. Genes & Dev. 2007; 21: 1443-1455.
- Convit A, Wolf OT, Tarshish C, de Leon MJ. Reduced glucose tolerance is associated with poor memory performance and hippocampal atrophy among normal elderly. PNAS. 2013; 100 (4): 2019-2022.
- Raji CA, Ho AJ, Parikshak N, Becker JT, Lopez OL, Kuller LH, Hua X, Leow AD, Toga AW, Thompson PM. Brain structure and obesity. Hum Brain Mapp. 2010; 31(3): 353-364.
- Zammit C, Liddicoat H, Moonsie I, Makker H. Obesity and respiratory diseases. Int J Gen Med. 2010; 3:335-343.
- Spitznagel MG, Alosco M, Strain G, Devlin M, Cohen R, Paul R, Crosby RD, Mitchell JE, Gunstad J., Cognitive function predicts 24-month weight loss success following bariatric surgery. Surg Obes Relat Dis. 2013; 9(5): 765-770.
- John Gunstad, Gladys Strain, Michael J. Devlin, Rena Wing, Ronald A. Cohen, Robert H. Paul, Ross D. Crosby, James E. Mitchell, 2011, ‘Improved memory function 12 weeks after bariatric surgery’, Surgery for Obesity and Related Diseases, vol. 7, no. 4, pp. 465-472
- Michael L. Alosco, Mary Beth Spitznagel, Gladys Strain, Michael Devlin, Ronald Cohen, Robert Paul, Ross D. Crosby, James E. Mitchell, John Gunstad, 2013, ‘Improved memory function two years after bariatric surgery’, Obesity, vol. 22, no. 1, pp. 32-38
- Furukawa S, Fujita T, Shimabukuro M, Iwaki M, Yamada Y, Nakajima Y, Nakayama O, Makishima M, Matsuda M, Shimomura I. Increased oxidative stress in obesity and its impact on metabolic syndrome. J Clin Invest. 2004; 114(12): 1752-1761.
- Mitchell JE, de Zwaan M. Psychosocial assessment and treatment of bariatric surgery patients. 2011;6: 103-109.
- Nguyen JCD, Killcross AS, Jenkins TA. Obesity and cognitive decline: role of inflammation and vascular changes. Front Neurosci. 2014; 8: 375.
- Chan JSY, Yan JH, Payne VG. The impact of obesity and exercise on cognitive aging. Front Aging Neurosci. 2013; 5: 97.
Shared Success Story – Albert L.
March 07, 2016 10:46 am
Lose weight, eat smaller portions, eat healthy, go to the gym, don’t eat bread, don’t eat starches, try this diet try that diet….. on and on.
It is so easy for dietitians, nutritionists, cardiologists, family members to speak these words. Being the one with the weight issue, it would drive me crazy hearing all the smart advice everyone had for me. I tried it all without success! Some for one day, some for longer, the results were always the same. I would lose a few pounds and in the end I would gain more. I imagine that the advice givers really didn’t understand the fatigue and appetite that comes with the extra pounds. At 39 years old, 245lbs, on blood pressure and cholesterol meds, all I could see was a life of diabetes and heart disease. Oh, the days I spent in department stores looking at designer clothes I couldn’t wear, talking to women who wouldn’t see past my belly, being the guy at the pool with his shirt on and most of all facing a very rocky future.


The day I walked into Dr Keshishian’s office was the day my life changed. He looked me in the eyes and told me it’s all going to be better. I had my surgery in June and my recovery was unusually fast. The pounds were dropping daily and within 6 weeks my cardiologist took me off my blood pressure and cholesterol medications. At eight months after surgery, I am so close to my goal of 180lbs. I have to admit that I would have reached my goal months ago. But a trip to Australia, wining and dining my new fiancé put me off track. But I’m happy to say I’m well on my way to success. Because I am feeling so much healthier, I have joined a gym. Since surgery, I don’t have a huge appetite so I am eating smaller and healthier portions. The future is looking very very bright. Thank you Doc.”
-Albert L.