
Tag: Weight loss surgery
Evaluations of Gallbladder Disease And Function
April 11, 2015 7:03 am
Gallbladder disease can include both anatomical and functional condition. We are familiar with gallstones. Bile acids, Lecithin (a phospholipid), and cholesterol are present in the Bile. When the proportional percentage of each one of them is outside a very narrow range, gallstones are formed. Approximately 75% of the gallstones are formed because of the supersaturation of the content of the gallbladder with cholesterol which results in cholesterol stone formation. The rest are pigmented stones.
Gallstones are usually identified by ultrasound and they are seen as shadows.
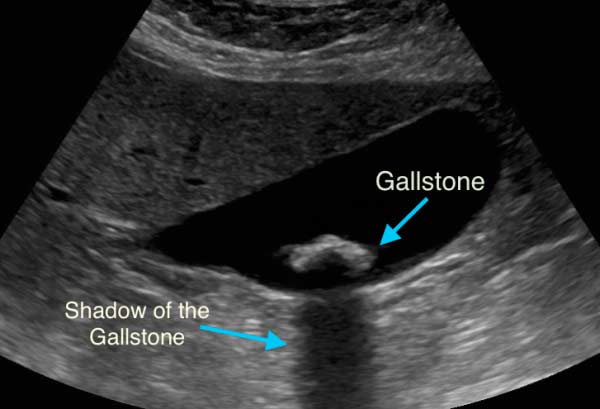
There are patients that have a normal gallbladder ultrasound result that continue to have signs and symptoms of gallbladder disease, such as abdominal pain in the right upper quadrant, nausea and vomiting with fatty meals, and bloating to name a few. These patients should be evaluated by a dynamic HIDA scan.
A dynamic HIDA scan study evaluates the function of the gallbladder, by creating a movie of the gallbladder, where as an ultrasound takes pictures of the gallbladder.
In a dynamic HIDA scan, and contractility of the gallbladder is reported in form of ejection fraction (%EF). This represent the amount of gallbladder contraction in response to the stimulation by a fatty meal mediated thru cholecystokinin (CCK). A normal EF is greater that 35%. Anything less than than with the sign and symptoms of gallstones, should be highly suspect for acalculous cholecystitis. Calculus because there is no stone.
(The bright white collection represents the filling of the gallbladder)
This short movie represents the uptake of the radio nuclear material in the gallbladder and its normal secretion in the small bowel.

These are the static images before the injection of CCK.
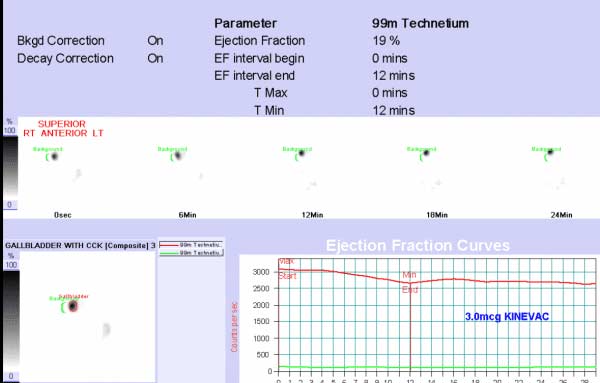
Following the injection, digital subsection of the images measure the amount of nuclear activity of the gallbladder before and after contraction and an Ejection Fraction is calculated.
First Duodenal Switch Patient- Dr. Hess
April 05, 2015 3:35 pm
I had the opportunity to be in a meeting with Dr. Hess in November of 2004. He presented a lecture about the history of the Duodenal Switch and his collaborative work with Dr. Scopinaro, the pioneer surgeon of the Biliopancreatic Diversion. The BPD was the the foundation of the Duodenal Switch operation. The first patient ever to have had the Duodenal Switch was a revision from a failed vertical banded March of 1988 by Dr. Douglas Hess. At the time of this particular meeting (in 2004), the patient was 17.5 years post op.

This is a copy of the slide that he shared with the surgeons present at the Duodenal Switch meeting on November 21, 2004.
Gall Bladder- Should the Gall Bladder Be Removed During Duodenal Switch?
February 16, 2015 1:17 pm
The indication for concurrent cholecystectomy (gall bladder removal) with weight loss surgery is not clear. There is some scientific literature that recommends against cholecystectomy at the time of the Gastric Bypass RNY operation. To the best of my knowledge, there is no such studies looking specifically at the indication of cholecystectomy with duodenal switch operation.
My rationale for doing a cholecystectomy with every Duodenal Switch patient is that there is not only higher incidence of asymptomatic cholecystitis present but also due to limited access to the biliary tree. The transection of the duodenum and removal of the greater curvature of the stomach both limit access to the biliary tree. Additionally, the patient recovering from weight loss surgery, may not be in the best nutritional status to undergo a subsequent operation for gallbladder removal. A second surgery could add to nutritional issues due to protein needs for healing, risk of infection, hernia formation, etc.
From a technical aspects, in Duodenal Switch operation, the liver and the gall bladder need to be elevated in order to expose the anterior surface of the duodenum where the transection of the duodenum is performed. Doing a cholecystectomy at the time of the duodenal switch operation, more often than not only add a few minutes to the operation. In the majority of patients, long-term this saves them the potential need for a subsequent operation at a later date should they develop gallstones or gall bladder attack.
When I perform a Sleeve Gastrectomy the duodenum is not transected or dissected, and thus I do not remove the gall bladder when doing sleeve gastrectomy. I do, however, remove the gall bladder when doing primary Duodenal Switch for revision from a Gastric Bypass RNY to the Duodenal Switch operation.
Telogen Effluvium: Hair Loss After WLS (Weight Loss Surgery)
September 14, 2014 12:56 pm
Telogen Effluvium is the premature pushing of the hair root into a resting state and can be chronic or acute. It is usually brought on by a shock to your body such as high fevers, childbirth, severe infections, severe chronic illness, severe psychological stress, major surgery or illnesses, over or under active thyroid gland, crash diets with inadequate protein, and a variety of medications. Most hair loss from medications, is this type of hair loss, and the related medications include retinoids, beta blockers, calcium channel blockers, antidepressants, and NSAIDS (including ibuprofen). Supplements that can also cause or increase telogen effluvium are higher doses of iron and Vitamin A.
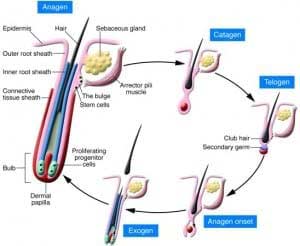
The hair begins to fall out in differing amounts and can start weeks to months after the initial shock to the body or medication initiation. The hair loss can continue up to 6 weeks and typically slows at 8 weeks after the start of the hair loss.
Weight loss surgical patients experience this due to the stress of surgery and the low protein state directly after surgery. Although there is no specific treatment for Telogen Effluvium, there are steps that can be taken to potentially slow the hair loss and help support the new hair growth.
The most important steps to take are to maintain your protein supplementation at a minimum of 80-100 grams of protein daily and hydration (at least 64 ounces daily) after weight loss surgery.
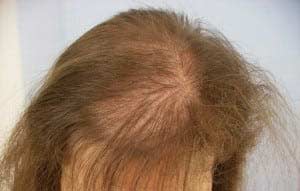
Protein, particularly L-lysine, are the building blocks of hair and nails, without adequate protein your body will forgo making hair and nails to maintain critical muscle mass. Also hydration is important to flush the body of toxins, due to fat breakdown in the liver during the rapid weight loss phase, that will prevent further new hair growth.
Vitamin B6 and B12 deficits can also contribute to hair loss. Multivitamin supplementation is essential to maintaining the required levels of these vitamins. The recommended multivitamin supplementation is two multivitamins daily that are equivalent to Centrum brand multivitamin.
Some people add Zinc supplements to increase hair production. However, if you are adding Zinc it is advised to also add a Copper supplement as they compete with each other for absorption. Copper is important for red blood cell production and a copper deficiency can exacerbate iron deficiency anemia. Inactivity can also decrease zinc levels, therefore exercise/activity will naturally maintain zinc levels.
Biotin is also a B vitamin that can be helpful in new hair growth.
Folicure is a supplement tablet that contains many vitamins and minerals that some people find helpful for hair re-growth. They also manufacture a shampoo that can be used.
There are many shampoos and topical treatments that people use and report satisfaction in their results. However, it is important to note that a topical treatment may make your hair appear thicker but the hair regrowth will only be supported by internal nutritional maintenance. Minoxidil is a liquid vasodilator medication applied to the scalp that is the exception to this rule and can help with hair regrowth. However, Minoxidil will not work to it’s optimal level in the absence of adequate nutritional status.
We always go back to our basics after weight loss surgery of hydration, protein and exercise to maintain health of body and hair.
September 3, 2014 Group Meeting & Webinar Laboratory Studies and Vitamin K2Exclusive Member Content
September 06, 2014 8:03 pm
Mission Statement
August 14, 2014 1:15 pm
Mission Statement for Central Valley Bariatrics and Dr. Ara Keshishian “The best patient that I can have is the most knowledgeable patient”
This is one of the “lines” that I use during my teaching and consultations sessions. I firmly believe that a patients should have all the pertinent information before they decide to proceed with a treatment plan. Be the treatment is medical in nature or surgical the patient needs to have all the scientific facts before an informed decision is made.
Part of my duty is to provide the information in a scientific and concise fashion in non-medical terms. Additional resources, such as this blog, FB group (The one managed by our office, and those maintained by others) along with the Webinar hosted by us, all serve to complement each other for providing a forum for exchange of information.
The value of information exchanged between patients can not be underestimated. Patients who have walked the path can provide a much more practical experience that I can ever share with a patient. The information shared between patient can and should carry a wider range of topics. It is to be noted however, that no information exchanged between patients should replace the advice of a patients’ surgeon.
For most of us that offer weight loss surgery, we realize that there is a lot more to the care of our patients that just to “cut” and hope for the best! The best outcome is dependent as much on the follow up care as it is to the surgery itself.
I personally believe that the care should be compassionate, respectful, caring and professional. There is no reason why the advice given should include disrespectful, or otherwise demeaning comments, suggestions or innuendoes. These have always been the guiding principals based on which we will conduct our practice on the Facebook, our blog and in person. No one, be patients, my office staff or myself should tolerate any personal threats, foul language or disrespect. For those who may see values to demeaning and inflammatory discussion tones, I wish you the best in other venues.
Ara
July 2, 2014 Group Meeting Recap
July 03, 2014 7:11 am
First and foremost, We apologize for the confusion and last minute change with the webinar. It was set to go and logged in then the internet dropped the group meeting. The meeting site automatically marked the meeting as over. We sent out e-mails with the new URL for the group meeting but it took time. Thank you for your patience with this new platform. Although far reaching, it comes with downsides and hopefully we can make this a long term way to reach our patients. Lesson learned, don’t rely on wireless internet access for webinars. The Anemia slides will be added to our website dssurgery.com soon.
Ferritin is a protein that acts like your savings account. It’s like a holding tank. When you have a blood loss your body goes to Ferritin stores for iron to increase red blood cell production. Iron is like money in your pocket. For small and daily building of red blood cells. Transferrin is a protein transport that carries the iron. Copper is also needed to transport iron. Iron can be readily available but will not be utilized unless your protein levels are adequate. The protein level on laboratory studies needs to be at least 6 gm/dL & Albumin 3.2 gm/dL for adequate iron utilization. Vitamin B12 also is needed for iron utilization.
Iron metabolism in the DS patient is limited due to several factors. In unaltered anatomy Iron enters the stomach where it is exposed to acid and changes into a form which allows it to be absorbed. Then it enters the duodenum which is the chief area of the small intestines where iron absorption takes place. There is possibly a second minor site of absorption near the end of the ileum. However, after the DS there is a small portion of the duodenum that is left after the pyloric value for iron absorption. Below is a list of iron rich foods. Also remember to take Vitamin C with your iron supplements and when eating plant based iron rich foods add a food that is high in Vitamin C.
There was a brief discussion regarding Calcium oxalate kidney stones. That talk can be found on our website. Treatment is limiting oxalate containing foods and to increase calcium supplements to 3,000mg daily but to take half with food and the other half without food. Also Vitamin K2 can also decrease kidney stones.
Fissures where also briefly discussed. Fissures are most likely caused by the unopposed bile salts entering the colon after DS. Bile is alkaline and causes irritation to the mucosa. Treatment is liberal use of barrier type creams/ointments, controlling loose stools by watching if certain food items cause them or by using fiber with half the liquid mixed with it. The fiber with less liquid acts as a sponge to give more form to the stool.
We had anemia themed snacks at the live group meeting. Pate, Southwest ground Bison, and a Mayan Pumpkin seed dip. Here is the information on the nutritional value of Bison versus other meats. It is higher in iron and Vitamin B12 and lower in fat and cholesterol.
Iron Content of Common Foods
This chart shows the amount of total iron in food. Iron from most animal sources (heme iron) usually is more readily absorbed than iron from plant sources of food (non-heme iron). Include a source of vitamin C or heme iron to improve the absorption of non-heme iron.
Sources of Predominantly Heme Iron
|
FOOD
|
IRON (MILLIGRAMS)
|
|
Beef liver, braised (3 oz)
|
5.8
|
|
Lean sirloin, broiled (3 oz)
|
2.9
|
|
Lean ground beef, broiled (3 oz)
|
1.8
|
|
Skinless chicken breast, roasted dark meat (3 oz)
|
1.1
|
|
Skinless chicken breast, roasted white meat (3 oz)
|
0.9
|
|
Pork, lean, roasted (3 oz)
|
0.9
|
|
Salmon, canned with bone (3 oz)
|
0.7
|
Sources of Non-Heme Iron
|
FOOD
|
IRON (MILLIGRAMS)
|
|
Fortified breakfast cereal (1 cup)*
|
4.5 – 18
|
|
Pumpkin seeds (1 oz)
|
4.2
|
|
Blackstrap molasses (1 Tablespoon)
|
3.5
|
|
Soybean nuts (1/2 cup)
|
3.5
|
|
Bran (1/2 cup)
|
3.0
|
|
Spinach, boiled (1/2 cup)
|
3.2
|
|
Red kidney beans, cooked (1/2 cup)
|
2.6
|
|
Prune juice (3/4 cup)
|
2.3
|
|
Lima beans, cooked (1/2 cup)
|
2.2
|
|
Tofu, firm (1/2 cup)
|
2.0
|
|
Enriched rice, cooked (1/2 cup)
|
1.4
|
|
Pretzels (1 oz)
|
1.2
|
|
Whole-wheat bread (1 slice)
|
0.9
|
|
Green beans, cooked (1/2 cup)
|
0.8
|
|
White bread, made with enriched flour (1 slice)
|
0.8
|
|
Egg yolk, large (1)
|
0.6
|
|
Peanut butter, chunky (2 tablespoons)
|
0.6
|
|
Apricots, dried (3)
|
0.6
|
|
Zucchini, cooked (1/2 cup)
|
0.3
|
|
Cranberry juice (3/4 cup)
|
0.3
|
|
Unenriched rice, cooked (1/2 cup)
|
0.2
|
|
Grapes (1/3 cup)
|
0.1
|
|
Egg white, large (1)
|
From: The American Dietetic Association’s COMPLETE FOOD & NUTRITION GUIDE, 2nd ed. 2002.
USDA National Nutrient Database
Shared Success Story: Cyndi E. Had a Gastric Bypass to Duodenal Switch Revision
June 17, 2014 6:29 am
My journey to lose weight has taken most of my life. Losing weight is not just about food or eating too much, but a combination of genetics, emotions, and habits. My experience began at age 13 and has continued throughout my life. I have tried everything! I had a previous RNY Gastric Bypass, and knew something was wrong. I had seen another Bariatric surgeon who said there is nothing I can do for you because you failed. My primary Doctor asked me “does your husband love you?” Of course, but what does that have to do with me knowing there is something medically wrong with me? Again, I was brushed off and told to come back in two weeks. Leaving that day, I knew I was never going back. I went home and googled, “Bariatric Surgeon”, as I had for the past 3-4 years. Then, through a series of events was put in touch with Barbara Metcalf, a bariatric nurse, who lived in my town. As I explained my story to Barbara, she shared information with me about Duodenal Switch operation, and gave me names of two surgeons.

I contacted Dr. Ara Keshishian, in Glendale, and had a consultation that week. Meeting “Dr. K” was amazing! It was the first time a Doctor did not blame me for my weight. He explained that each weight loss surgery has different measures of success, percentages of weight loss by surgery, and outcomes. Dr K told me that I may have been a success with the RNY Gastric Bypass, based on the numbers, however it became clear that I did have complications associated with the gastric bypass. I was scheduled for an Endoscopy the next week, which Dr. K performed. The endoscopy confirmed that I had a Gastro-gastric Fistula. Simply put, this was an abnormal connection between the bypassed stomach and the small pouch created by the RNY Gastric Bypass surgery. Food could travel two ways, thus rendering the Gastric Bypass ineffective, and causing weight gain.
Dr. Keshishian performed a revision to the Duodenal Switch Surgery on May 31, 2013. This procedure corrected my anatomy, enabling me to lose weight and regain my health once again. I have had wonderful success and I have lost 104 pounds. More importantly, I do not have the complication of the dumping syndrome, episodes of nausea and vomiting and am leading a normal life. I am not prisoner to my weight, what I can and cannot eat or the fear of weight gain.

I contacted Dr. Ara Keshishian, in Glendale, and had a consultation that week. Meeting “Dr. K” was amazing! It was the first time a Doctor did not blame me for my weight. He explained that each weight loss surgery has different measures of success, percentages of weight loss by surgery, and outcomes. Dr K told me that I may have been a success with the RNY Gastric Bypass, based on the numbers, however it became clear that I did have complications associated with the gastric bypass. I was scheduled for an Endoscopy the next week, which Dr. K performed. The endoscopy confirmed that I had a Gastro-gastric Fistula. Simply put, this was an abnormal connection between the bypassed stomach and the small pouch created by the RNY Gastric Bypass surgery. Food could travel two ways, thus rendering the Gastric Bypass ineffective, and causing weight gain.
Dr. Keshishian performed a revision to the Duodenal Switch Surgery on May 31, 2013. This procedure corrected my anatomy, enabling me to lose weight and regain my health once again. I have had wonderful success and I have lost 104 pounds. More importantly, I do not have the complication of the dumping syndrome, episodes of nausea and vomiting and am leading a normal life. I am not prisoner to my weight, what I can and cannot eat or the fear of weight gain.
Sunshine, Water, Rest, Air, Exercise and Diet
May 23, 2014 4:10 pm


Sunshine, Water, Rest, Air, Exercise and Diet
Of course this is over simplified, but we can’t forget the importance of the basics in our general well being. Weight loss surgery and especially Duodenal Switch have distinctive supplement requirements that need to be individualized based on your individual needs.
Sunshine is essential to life. It provides the light that wakes us and helps to regulate wake/sleep cycles and provides us with a feeling of well being. Sunlight is not only the basis of all living things but crucial in boosting the bodies Vitamin D supply. Most Vitamin D deficiencies in the general public are caused by lack of sun exposure. It is important to note that our bodies can not accomplish Vitamin D metabolism if we are wearing sunscreen. Without adequate Vitamin D stores bones will not form properly, muscle strength is impaired and osteoporosis. Vitamin D 1,25(OH) accumulates in cell nuclei of the intestine, where it enhances calcium and phosphorus absorption, controlling the flow of calcium into and out of bones to regulate bone-calcium metabolism. However, after weight loss surgery this mechanism can be impaired. Addition supplementation of Vitamin D is usually required based on laboratory studies following weight loss surgery. Duodenal Switch patients should take a dry “water miscible” type of Vitamin D3 daily.
Water comprises 50-60% of our adult bodies. Water is essential in cell life. It aids in transporting vitamins, nutrients and minerals to our cells. Chemical and Metabolic reactions rely on water to remove waste products including toxins that the organs’ cells reject and removes them through urine and feces. Our body temperature is regulated by sweating and the evaporation of water on the skin. Also, effectively Lubricating our joints and acting as a shock absorber for our brain, eyes, and spinal cord. Decreased stomach size, after weight loss surgery, limits the amount of water a person can drink at one time. It is imperative that patients ingest enough waters and fluids after surgery. We like to see our patients consume a minimum of 64 ounces of fluids a day, more on warmer days.
Rest is something we can all use more of. Lack of sleep can cause a whole host of health issues ranging from altered levels of hormones involved in metabolism, appetite regulation, stress response to cardiovascular health, insulin resistance, immune function and most importantly post-operatively tissue repair, muscle growth and protein synthesis. It’s easy to take rest for granted but do not underestimate the power of sleep.
Air is an obvious essential of life. It is important in about every function of our cells. After surgery it is important to lung health and tissue repair. Be aware of the type of air you are breathing. Pollution and contaminants in the air can impair lung function. After surgery your breathing and breathing exercises will prevent complications such as pneumonia and atelectasis. Long term air contaminants can cause asthma and long term lung health. In addition, post surgical patients will need to use their incentive spirometers to combat lung complications.
Exercise’s health benefits can not be denied. Exercise combat health conditions and disease such as stroke, metabolic syndrome, diabetes and cardiovascular disease. It also improves emotional outlook and mood. Physical activity stimulates the brain to release chemicals that involve increasing memory function. Exercise helps maintain healthy weight, improves energy, promotes better sleep, lowers stress and anxiety. Needless, to say after surgery exercise is extremely important for all the above reasons but also to ward off complications such as pulmonary embolism and deep vein thrombosis.
Diet is last but definitely not least. Balance along with moderation and eating whole unprocessed foods are best ways to ensure your health. We derive most our building blocks for cell growth from the nutrients we consume. The quality of the food we put into our bodies is important in lowering health risks such as cardiovascular disease, cancer, and weight control. Protein is crucial in muscle growth, hemoglobin, cell structure and enzymes formation. It is extremely important after weight loss surgery to remain diligent about protein intake throughout your lifetime.
It is interesting to see how all these elements are so intertwined in their synergy to maintain health. Most are easily found or done in nature. When engaging in one of these elements, many of the others are needed or benefited by the doing the first. Exercise requires that you stay hydrated, deep breath, possibly out in the sunlight and therefore you will rest better. Always follow your surgeon’s orders and recommendations based on your individual health status and laboratory studies.
Our First Featured Success Story
May 16, 2014 9:47 am
Patricia Welborn
