
Vitamin D And A -Dry (Water soluble) Formulary
August 24, 2013 7:57 pm
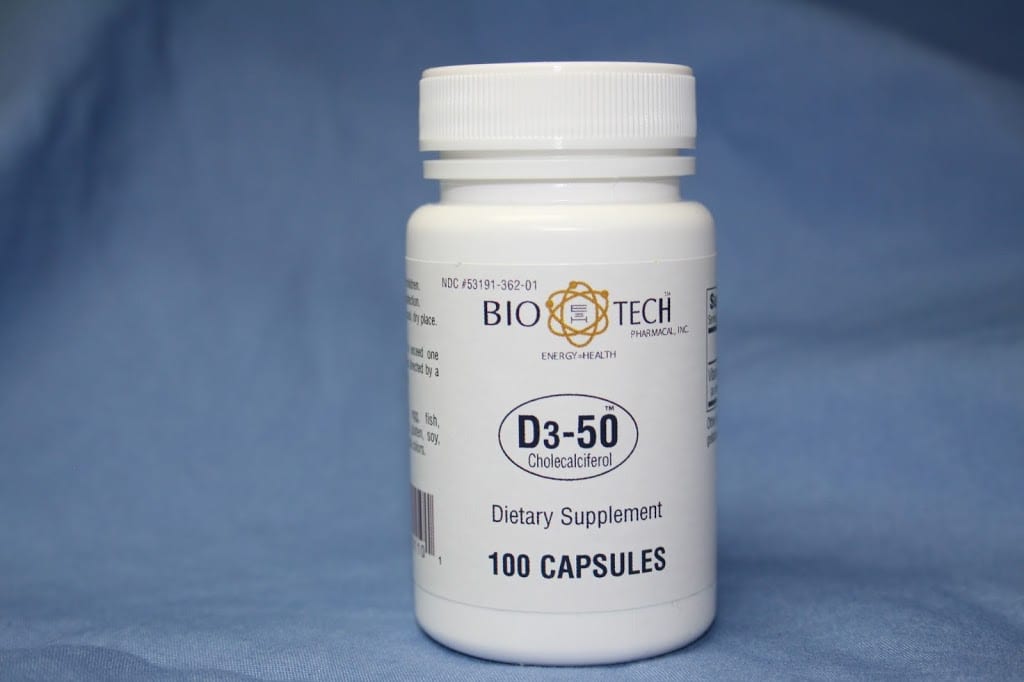
Vitamin A and D are fat soluble vitamins. This means that in order for them to be absorbed by the GI track, them need to be absorbed by fat globules (chylomicrons). These are then taken up by the lymphatics of the GI track and taken to the blood stream. With the anatomical changes of the Duodenal Switch, the fat absorption capacity is significantly reduced. This results in excellent weight loss. It also results in much diminished absorption of the Fat soluble vitamins A, D, E and K. It is essential to use Dry Water Soluble forms of Vitamins A, D, E, and K. Bio-Tech is a brand that is formulated in this manner.

The Biotech D3-50 has 50,000IU of Vitamin D.

We recommend specific dosages of dry (water soluble) Vitamin A and D. These are not available at most pharmacies. In fact when our recommendations are presented at most pharmacies they are incorrectly dispensed with the fat soluble variety with is worth less becasue it is not absorbed by the duodenal switch patients. It is also important to not that this type of vitamin should not be taken with any dietary fat. Fat can inhibit the absorption of this type of vitamin. When ordering online, please make sure that the “Dry” or “Water Soluble” formulary is ordered.
Injectable Vitamin A and Vitamin D
June 20, 2013 11:24 pm
Injectable Vitamin A and Vitamin D can improve vitamin status post weight loss surgery. One of the common side effect of all weight loss surgical procedures is nutritional and/or mineral deficiencies. Patients undergoing weight loss surgical procedures are always instructed to supplement their diet with multivitamin, calcium, iron, vitamin D and other supplements or minerals. If you do not take your supplements regularly you can become deficient. The symptoms associated with vitamin A deficiency is night blindness. Chronic vitamin D deficiency may result in low calcium, osteoporosis and other health-related issues.
Vitamin A and vitamin D, both fat-soluble vitamins, are absorbed by duodenal switch patients only if taken and a dry formulation. An alternative to oral supplement, would be injectable form of these two vitamins. Both of these vitamins can be formulated and purchased from compounding pharmacies that are equipped and experienced with the interpretation of injectable vitamins and minerals. Your primary care WILL need to contact the pharmacy of their choice for the recommendations and be willing to make the injections available to you.
We will gladly be able to provide injectable Vitamin A and Vitamin D for patients whose data laboratory studies are available to us and see us in the office.Please be aware that these are compounded and are not covered by insurance.
We will not be able to provide prescriptions for injectable vitamins to be sent to your primary care or other physicians to provide the injections.
Vitamin D supplement has been discussed previously in my Blog .
The common dosing for the vitamin D is 600,000 IU, deep IM every 6 months till the levels are normalized. The patient then can take the oral supplements only.
Vitamin A supplements was also discussed in my Blog.
The common dosing for the vitamin D is 100,000 IU, deep IM every 2-6 months till the levels are normalized. The patient then can take the oral supplements only.
Vitamin A supplements was also discussed in my Blog.
The common dosing for injectable vitamin A is 50,000 IU, deep IM every 6 months till the blood levels are corrected, and the patient symptoms are resolved.
Just as a reminder, we have no financial interest in any of the vendors that are recommended on our website. Also, note that this is not in any form or fashion a substitute for an evaluation by your primary care physician or your surgeon. This is for information only, and is not to be taken as a recommendation for any particular patients’ condition.
Gastro-gastric fistula after gastric bypass operation
May 10, 2013 9:09 pm
One of the complications of gastric bypass is a gastro gastric fistula. This happens when a connection between the gastric bypass pouch develops to the remnant stomach. In a gastric bypass operation, a very small pouch is created from the stomach, and connected to a segment of the small bowel.
The purpose of this operation is to decrease over 95% of the volume of the stomach. In theory, the benefits of this is to reduce the volume of food that can be consumed. Over time, the size of the stomach pouch, and/or size of the gastro-jejunostomy anastomosis might stretch. This result in weight regain that is very commonly seen in about 3 years after a gastric bypass operation.
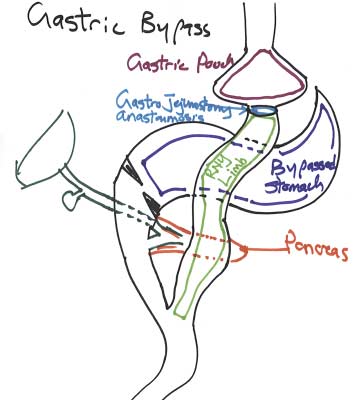
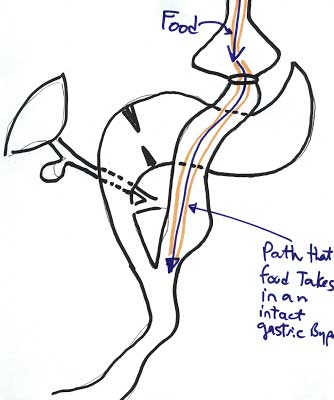
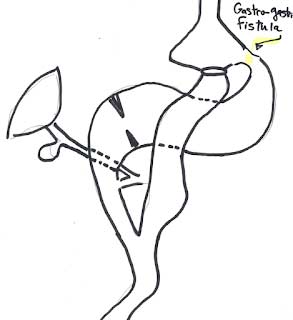
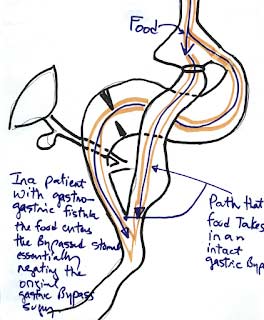
One of the complications of gastric bypass is a gastro gastric fistula. This happens when a connection between the gastric bypass pouch develops to the remnant stomach. In a gastric bypass operation, a very small pouch is created from the stomach, and connected to a segment of the small bowel.
The purpose of this operation is to decrease over 95% of the volume of the stomach. In theory, the benefits of this is to reduce the volume of food that can be consumed. Over time, the size of the stomach pouch, and/or size of the gastro-jejunostomy anastomosis might stretch. This result in weight regain that is very commonly seen in about 3 years after a gastric bypass operation.
Another possible explanation for weight regain may be an abnormal connection that may develop over time between the bypassed stomach and the small pouch that was created. This abnormal connection is known as a gastro-gastric fistula. In a patient who may have a gastro-gastric fistula, the food can travel down the gastric bypass path or enter the bypassed stomach and go down the path of a normal anatomy.
In these cases, the physiological effect of a gastric bypass procedure becomes ineffective.
The treatment that I favor most for correcting the complication of the gastro-gastric fistula is is to revise the gastric bypass to the duodenal switch operation.
“Normal” Lap Band placement!
April 23, 2013 9:39 pm
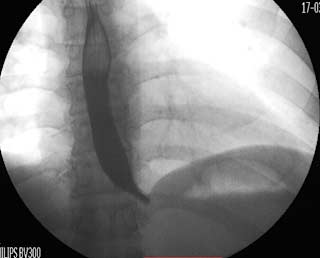
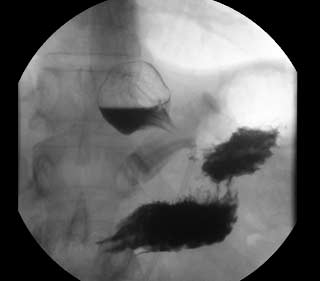
One of the most common problems that we see are patients who have been told that their band is in correct placement, and yet they are still having nausea, vomiting, reflux etc. These patients are frequently blamed for their symptoms as if properly placed band completely eliminates the problems being associated with the band.
Stages of Liver Failure
January 08, 2013 9:38 pm
The liver is probably one of the most forgiving organs when it comes to recovering from an injury. It can take a significant amount of “non structural” injuries and still be able to carry out its function. It is the only solid organ capable of regenerating its volume after a major resection. When a part of the liver is removed, it is within a matter of months that the size of the remaining liver increases to replace the removed portion.
A liver injury can be caused by a number of elements. In regards to weight loss surgery, these elements include alcohol consumption, high doses of Tylenol, excessive weight loss, and the most significant condition called steatohepatitis, also known as “fatty infiltration”. Steatohepatitis causes structural changes in the liver. Over time, the structural changes cause the liver to progress to an end-stage liver disease that requires a transplant. Structural changes to the liver injury are irreversible.
The healthy liver is normally soft and beefy-red with a very smooth and shiny outer layer.
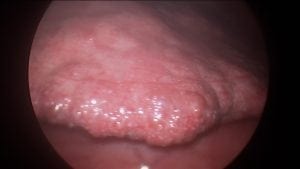
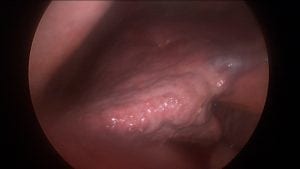
How does steatohepatitis harm the liver? As the fat concentration of the liver increases, the liver loses its sharp edge and becomes distended with small pockets of fat that are visible as yellow satellite lesions.
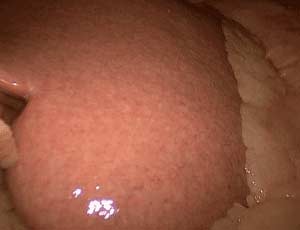

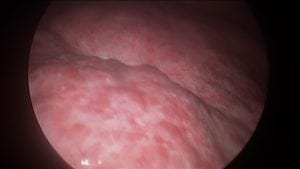
The healthy liver is normally soft and beefy-red with a very smooth and shiny outer layer.
How does steatohepatitis harm the liver? As the fat concentration of the liver increases, the liver loses its sharp edge and becomes distended with small pockets of fat that are visible as yellow satellite lesions.
This is gross evidence of steatohepatitis, which is commonly known as fatty infiltration of the liver. The most common cause of this is obesity, in addition to medications such as insulin that are used to treat diabetes. If the underlying cause of steatohepatitis is not addressed, then the liver damage will progressively continue to worsen and eventually be resolved in the structural changes to the liver.
If the physiologic injury to the liver continues unabated, it will develop irreversible cirrhosis. An increasingly continuous insult to the liver will result in sudden liver failure, which will require a liver transplant.
Emergencies of Adjustable Gastric Banding
November 14, 2012 2:07 am
Adjustable Gastric Banding (AGB) procedures have been presented and promoted as innocuous and low risk in nature. AGB still carries significant risks although its perioperative complication rate appears to be less compared to other weight loss surgical procedures. Such risks include permanent and potentially life-threatening damages or other complications if proper treatment isn’t sought in an urgent manner.
Often times a patient’s complaints are minimized and blamed on behavior or their presumed non-compliance. Quite frequently they are only referred to a surgeon after exhaustive workup has been completed and mostly reported back as normal. These workups include upper GI series and endoscopic studies. Nevertheless, the complication(s) with which a patient may have been presented with still continue.
I would like to discuss two such examples in which patient care may have been delayed.
The first patient was a 45-year-old male who had the AGB procedure completed approximately two years prior to her first visit to our office. He presented complaints of abdominal pain and worsening reflux. He had had multiple adjustments at his primary surgeon’s office and was told to be in the optimal “green zone” for the band. He had lost approximately 45% of his excess weight, but continued to have significant debilitating reflux.
An upper endoscopy was reported to be normal and consistent with a properly placed band. An upper GI performed months later identified a dilated esophagus, requiring the band to be removed. In hindsight, the band should have been completely emptied upon the patient’s first complaints of abdominal pain and reflux.
The next patient visited a local emergency room with acute onset of nausea and vomiting. She was sent home with a diagnosis of gastroenteritis and instructed to follow up with her primary care physician. She returned back to the emergency room within 36 hours with a progressively worsening nausea and vomiting. She was admitted and underwent an upper endoscopy after which a surgical consultation was obtained. The patient was taken to the operating room with a diagnosis of “slipped band”, and had to have the band removed emergently. Looking back at this case, the abdominal x-ray was suspicious for a slipped band. She should have been referred for surgical care at the time of her first emergency room visit.
Ultimately, the burden of proof is on the medical provider treating the patient with an AGB to ensure that there is no slippage when the patient presents with acute changes in his or her condition. The AGB may still “appear” to be in the proper place and adjusted with the patient still having symptoms of reflux, inadequate weight loss, and abdominal pain. These patients would require surgical intervention and probably removal of the band.
As indicated earlier, the patients’ complaints should not be discounted as being a compliance issue and instead should be referred for surgical evaluation.
Slipped Band
November 02, 2012 10:40 pm
Duodenal Switch Procedure
September 16, 2012 1:16 pm
The Duodenal Switch procedure is a restrictive and malabsorptive weight loss surgery. Also, referred to as Gastric Reduction Duodenal Switch (GRDS).
Duodenal Switch Anatomy
1 – Restrictive Component
Approximately 70% of the stomach is removed along the greater curvature. This is also called a Vertical Sleeve Gastrectomy (VSG). The remaining stomach is fully functioning, banana shaped and about 3 – 5 oz. in size; which restricts the amount you can consume. The pylorus, part of stomach, continues to control the stomach emptying into the small intestine; as a result patients do not experience “dumping”. The upper portion of the duodenum remains in use; food digests to an absorbable consistency in the stomach before moving into the small intestine. Compared to gastric bypass procedures, this allows for better absorption of nutrients like vitamin B12, calcium, iron and protein. A benefit of removing a portion of the stomach is it greatly reduces the amount of ghrelin producing tissue and amount of acid in the stomach. Ghrelin is the “hunger hormone” and by reducing the amount the hormone produces, the appetite is suppressed. The stomach will stretch over time; 9-12 months post-op, it will eventually double in size and patients will be able to consume approximately 50% of what they did before surgery. The restrictive component of the Duodenal Switch procedure is not reversible.
2 – Malabsorptive Component
The intestines are re-routed so that food from the stomach, alimentary limb, and the digestive juices, biliopancreatic limb, that are needed for the absorption of fat and proteins can travel separate paths; this is so they don’t mix until they meet up towards the end of the small intestine.
The common channel, also known as the common tract or common limb, is the point from where the alimentary and biliopancreatic limbs meet in the small intestine to move into the large intestine. The common channel is where a DS patient’s food, bile and digestive juices mix; the majority of the fat, protein and the associated nutrients are absorbed. Since the common channel makes up such a small portion of the small intestine the dietary starches, fats and complex carbohydrates may not fully absorbed.
The most commonly quoted absorption percentages following DS are approximately 20% of fats, 60% of protein, 60% of complex carbohydrates, but 100% of simple carbohydrates. The 2005 study by Gagner et al. [68] demonstrated that DS surgery decreased fat absorption by 81%. The Bariatric Nutrition: Suggestions for the Surgical Weight Loss Patient review reports information from a study by Slater et al. stating that “After BPD/DS procedures, the amount of protein should be increased by ~ 30% to accommodate for malabsorption, making the average protein requirement for these patients approximately 90 g/d.” [65]
The malabsorption of fats interferes with absorption of the fat-soluble vitamins A, D, E & K. As a result all Duodenal Switch patients are required to take vitamin and mineral supplements for life. Patients must be diligent with the required supplements and have blood work monitored regularly. Also, they must adjust their supplements as needed to maintain normal levels of these vitamins and minerals.
The intestinal switch portion of the Duodenal Switch procedure is fully reversible.
Metabolic Effect
There is no dispute that Duodenal Switch produces the best-sustained weight loss, and has the best resolution rate for most comorbidities of all weight loss surgical procedures. These results cannot be simply explained by the restrictive and the malabsorptive component of DS. The general consensus is: that there are a number of hormonal regulatory changes involving Ghrelin, GLP-1, Enteroglucagon, Insulin, and others hormones (enzymes) that regulate the complex endocrine pathways.
Hess Method
Many often hear Duodenal Switch procedure patients using the term “Hess Method” [1] when discussing common channel length. Dr. Hess in Dublin Business News Monthly calculated the length of the alimentary limb by multiplying the total small bowel length by 40%. The remaining 60% of intestine carries the digestive juices through the biliopancreatic limb. The length of the common channel is approximately 10% of the total length of the small bowel. “Hess Method” refers to following Dr. Hess’s calculation for determining the limb lengths and common channel length, but other factors are taken into consideration; like the patient’s age, weight, BMI and goals. Each patient has a different length of common channel and alimentary loop designed to achieve the best results. “Length Measurement in Duodenal Switch” is discussed and explained in detail at https://www.dssurgery.com/procedures/streaming-media.php
Not all surgeons use the “Hess Method”, but some surgeon’s use a standard measure for the common channel of 100 cm and 150 cm, which is often used.
Ask a surgeon how he/she determines common channel length.
Appendix and Gallbladder
Some surgeons will remove the appendix because there is almost no extra effort that is placed in removal of the appendix, since the small bowel is measured from the junction of the colon and the appendix.
Few surgeons routinely remove the gallbladder because there is a 30-50% chance of gallstones forming after rapid weight loss. [56-57] For patients whose gallbladder is not removed often, medication is prescribed to help reduce the instance of gallstones from 30% to 2%. [57] One other compelling reason why the gallbladder should be removed is because of the inaccessibility of the biliary tree by a specialized endoscopic technique ERCP. The medication that is also prescribed has frequent side effects that limit their use and compliance with patients.
Staged Duodenal Switch
Duodenal Switch is sometimes performed in two stages when the surgeon determines it is too risky for the patient to undergo the whole procedure at once. This is usually a result of a patient’s age, BMI, comorbidities or for a more difficult revision surgery. The surgeon will perform stage one, restrictive component, then when the patient has lost some weight and the other health issues clear up then stage two, intestine switch, is performed.
For more information on the Duodenal Switch procedure:
Central Valley Bariatrics Graphical Comparison of Weight Loss Surgery Procedures
Revision or Reversal of the Duodenal Switch
September 08, 2012 7:00 pm
A significant portion of my practice involves the revision of the Gastric bypass and Adjustable Gastric Banding procedures to the Duodenal Switch operation. The re-operations are necessary to correct the complications that have been caused by these procedures. There are also instances of required revisions due to inadequate weight loss or weight regain. Our website contains detailed information regarding reasons for revision and the reversal of weight loss surgical procedures. I think it is important to mention that these complications are very common and almost never have anything to do with the patient’s behavior.
Duodenal switch operations may also require reversal or revision. The general reasons for a revision or reversal of the Duodenal Switch is the same as for all weight loss surgical procedures and include a variety of reasons. The reversal or revision of the Duodenal Switch operation is one of the simplest revision surgeries that I perform.
Let’s review a few facts about Duodenal switch.
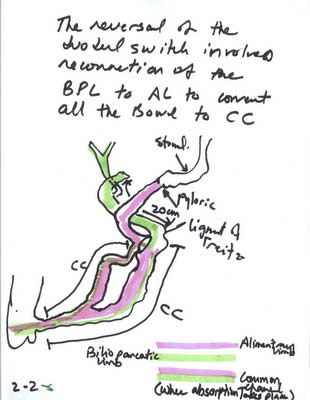
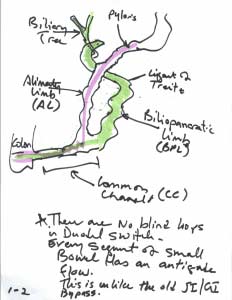
The Duodenal Switch procedures has two components:
1.) The sleeve gastrectomy
2.) The separation of the biliopancreatic secretions from the food to limit its absorptions.
Clearly, the portion of the stomach that has been removed cannot be reintroduced to the abdominal cavity. The second part of the operation can, however, be easily “undone.
The assumption is that the bowel needs to be divided again and re-anastomosed to reconstitute its continuity. This revision or reversal of the Duodenal Switch operation is done by simply creating a new connection between a new anastomosis, located between the biliopancreatic limb, and the alimentary limb.
If a complete reversal is needed, then the connection is made just distal to the ligament of Treitz. Ligament of Treitz is the transition point between the duodenum and Jejunum. This single anastomosis is safe and simple to perform and does not involve removing the previous staple lines.
If a partial revision is needed, or the common channel needs to be lengthened, then the anastomosis is made further proximal to the junction of both the alimentary limb and the biliopancreatic limb, but distal to the ligament of Treitz to allow for increased absorption of the calories and nutrientsIn my opinion, the revision and reversal of the Duodenal Switch operation is, from a technical perspective, the simplest of all revisional weight loss surgical procedures.
In my opinion, the revision and reversal of the Duodenal Switch operation is, from a technical perspective, the simplest of all revisional weight loss surgical procedures.
What is my target weight?Exclusive Member Content
August 24, 2012 12:31 am