
Our office is located at 5170 Sepulveda Blvd., Suite 210, Sherman Oaks, CA 91403. We accept select PPO insurance plans. For appointments and telehealth consultations, contact us.
1-818-812-7222 Office Hours: Monday Thru Friday: By Appointment only
5170 Sepulveda Blvd. Suite 210
Sherman Oaks, California 91403

Blog

Carbonated Drinks and Weight Loss Surgery

August 11, 2012 3:56 pm

The consumption of carbonated drinks is discouraged after weight loss surgery. In fact, there is a wealth of information that documents the detrimental health effects of carbonated drinks for each individual. These include osteoporosis, obesity, and premature dental decay, just to name a few.  Indirectly, carbonated drinks have been found to increase risk of stroke and Cardiac events. There are studies that show a 48% increase in heart attack and stroke rates for individuals who drink diet sodas vs. those who drink it rarely or not at all.

There is also no health benefit to diet carbonated drinks.  In fact, there are animal studies that show that rats who consume no-calorie sweeteners found in diet sodas experience an increased appetite (Susan Swithers, PhD- 2004).

There are also other factors to consider. The carbonation comes from a mixture of dissolved gasses that are released when the container is opened.  The Carbon Dioxide gas dissolved in the drinks, amongst others, can distend the stomach. Potentially, stretching your stomach. There is also acidity that needs to be corrected by the body. This has been shown to result in changes in the bacterial population in the GI track, resulting in significant bloating and reduced absorption of nutrients.

Calcium loss is caused by the leaching of the calcium from the bones with carbonated drinks, which can cause osteoporosis.

Nasal Methicillin Resistant Staphylococcus Aureus Predicts Site Infection In GI Surgery

August 06, 2012 12:27 am

Dr. Papaconstantinou of White Memorial Hospital in Temple, Texas has studied the relationship between the presence of colonized nares with Methicillin Resistant Staphylococcus Aureus (MRSA) and the incidence of the type of the infection after a gastrointestinal surgery.

He studied 1137 patients. He compared the postoperative infection rate of patients that were positive for MRSA, Negative for MRSA and a third group that was Methicillin Sensitive Staphylococcus Aureus (MSSA). He found that the infection rate for MRSA group was 14%, the highest of all the groups. There was no correlation however when other risk factors were accounted for.

The most significant finding however was the type of the infection present in MRSA patients. With positive nasal swab for MRSA, the most common organism causing the wound infection was MRSA (70%). In patients that were MRSA negative for the nasal swabs, the rate of MRSA wound infection was low at only 8.5%.

An additional finding was that the finding of MRSA positive nasal swab was a predictor for prolonged hospitalization.

There was no reported difference in the postoperative death rate in the MRSA positive or negative group.

It is important, however, to remind ourselves that this is a single study and more studies are needed to look at these variables in different surgical procedures.

The long-term outcome of the Adjustable Gastric Banding Esophageal Dilation after Gastric banding

July 07, 2012 12:35 am

The initial short-term data available for Adjustable Gastric Banding (AGB- Lap Band and Realize Band in the US) was promoted as a minimally invasive procedure with an equal outcome and low risk compared to the more commonly performed gastric bypass or the most successful procedure, the Duodenal Switch operation.

Over the years the data that has been published has drawn a completely different picture. The weight loss has not been as anticipated or sustained in majority of the patients who have had the AGB. Furthermore, the incidence of complication has been far worse than initially presented.

Common complaints that the patient reported with AGB includes inadequate weight loss, symptoms of reflux, abdominal pain, and significant solid or food intolerance. The general consensus and treatments have been tailored towards adjustment of the band either by adding fluid to tighten, to hopefully promote weight loss or by removing fluid from the band to reduce the restriction and resolving the reflux and/or deep abdominal pain. This only is after a mechanical or placement issue has been ruled out.

Most recently published data (Poster presentation ASMBS 2011 San Diego, CA.) shows that majority of the patients who developed esophageal dilatation, will require conversion to a different bariatric surgery. Furthermore, the consensus developing is that the placement of band should not be performed since there are better alternatives that can yield much better results with a safety profile that is better than that of the AGB.

As I have summarized previously, if long term data is reviewed the complication rate of the AGB is much higher that initially reported. I think there has been selective reporting of the data performed to promote a procedure that in the very short term may look attractive, however, over time, complications surface. Almost all patients with AGB procedures are sent home the same day, and in the first few months some weight is lost and almost no complication of reflux, indigestion, or other esophageal motility problems are reported. Yet when the same patient data is collected past the 12 months then there is increase in the reported cases of the complication of the banding procedures. This has lead to European and South American Centers that have lead the wave of the AGB placement to make a reversal of course and now recommend that other surgical procedures be offered to patients instead of the temporary fix of the AGB.
With our own practice we have significantly reduced the AGB placements. It is impossible to recommend a procedure that its results cannot be backed up with scientific data. We also find ourselves, spending a significant amount of time correcting the information that most patients have obtained from non-medical sources and even in some cases from other health care providers that is just not correct.

These are some of the examples of the information that I would like to clarify and explain to patients since they are deceiving and inaccurate.

“The band is reversible.”
Let’s take the concept of the “reversibility”. Can anyone name a procedure that a patient may need to have it done as a cure to an ailment with a condition of reversibility? Would anyone like to have a reversible hip replacement? Appendectomy? Or Cancer surgery? The point that I am raising is that the option of reversibility all by itself is not a meaningful measure other than it can be removed. One has to ask why I would want it removed. The answer is that it has a high complication rate that surface later on and in almost all cases requires band removal.

“It has minimal risk.”
The issue of the risk is one that I also emphasize. I think is inadequate to discuss the option of the risk in vacuum with no discussion of the benefits of each procedure. In majority of the cases patients indicate that the AGB can be done as outpatient (correct) with minimal down time (correct). The long-term outcome however is not there and I would recommend that the patient have no surgery since the long term complication of the banding is significant for any marginal benefit of weight loss.

“Patients have complications with the gastric stapling.”
There is a general misunderstanding that all procedures that have to do with weight loss are either the “gastric banding or the stapling type”. It is critical that we all appreciate that there are a number of different surgical procedures, that have different outcomes and each one of them needs to be examined for suitability for each patient

Bloating and Excessive Gas

April 17, 2012 7:36 am

The relationship between the consumption of food, bloating, and excessive gas is a subject that comes up frequently. In our practice, this is a complaint usually raised 3 or 4 years after receiving the duodenal switch operation. It appears that patients eventually disregard the recommendations made for a healthier diet of low carbohydrate, high protein, hydration, supplements, and then everything else.

In general, carbohydrates, carbonated drinks, artificial sweeteners (such as Splenda®, sugar alcohols, etc.), vegetables, excessive amounts of food, and an intake of fat will cause significant gas and bloating. This is not to be taken out of context and assumed that one cannot consume any of these products. However a diet that has fruits and vegetables will cause significant gas and bloating. These can not be controlled by probiotics, antibiotics, or other products such as Beano.

Simple carbohydrates/sugars (sugar, candy, cakes, cookies, pies, regular soda pop, jelly, jam, syrup, ice cream, sherbet, and sorbet, etc.) are easily absorbed. Simple carbohydrates/sugars can increase diarrhea due to the Duodenal Switch allowing more undigested sugars/fuel for intestinal bacteria to feed upon, multiply and form gas. The end result can be gas, bloating, and diarrhea.

Complex carbohydrates have more structure than simple carbohydrates/sugar which are harder for the intestinal bacteria to break down and may cause less bloating, gas and diarrhea. Also, complex carbohydrates usually contain higher fiber content.  The fiber in the colon will help to absorb water from the stool and can reduce diarrhea.  However, this is not the case for all Duodenal Switch patients.
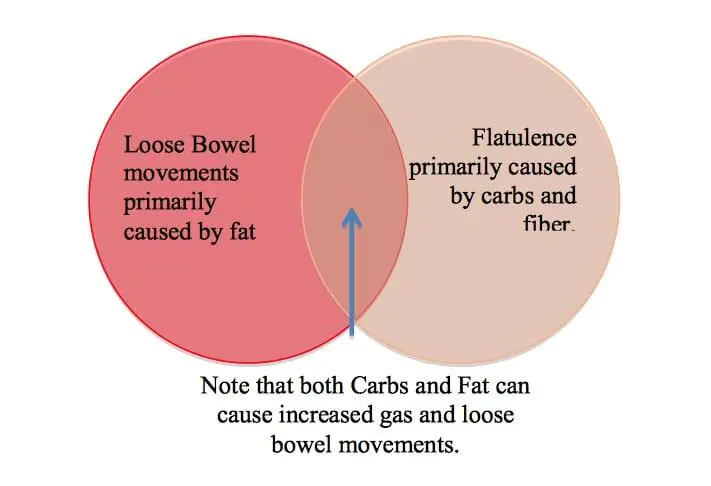
When a patient reports these problems, I recommend that the consumption of all carbonated drinks should be stopped. No patient should consume carbonated drink of any sort. Artificial sweeteners should also be avoided all together. A good alternative would be honey, maple syrup or Stevia. Minimize or reduce the carbohydrate intake.

It has been our experience in the majority of cases that excessive gas and bloating is a result of dietary indiscretion. In some patients, once the dietary sources have been ruled out, it should be further evaluated by a barium enema to rule out the diagnoses of a redundant colon.

The best approach would be to first go back to a high protein and low carbohydrate. This should allow a patient to rule out any dietary sources for the bloating and excessive gas. It is recommended to next be seen by your physician for a further workup.

To summarize, when a patient has excessive amount of gas, diarrhea and bloating, the first line of treatment is elimination of all of the possible causes. These include carbohydrates, fruits, vegetables, artificial sweeteners, carbonated drinks and milk products. I can not overemphasize the importance of this step prior to anything else such as antibiotics or probiotics.

Gastric Emptying after the Duodenal Switch and the Sleeve Gastrectomy

January 19, 2012 1:10 am

 
I am frequently asked what the transit time is from when the food is ingested to when the stomach empties. The emptying of the stomach depends on a number of complex factors, including the function of the pylorus, the type of food ingested, and a number of known and possibly unknown regulatory hormones.
In a previously published newsletter, we already discussed a number of hormones that play a role in the regulatory function of the GI track. The detailed information is posted in the newsletter section of our website.
 

Gastric emptying time after Duodenal Switch and Sleeve Gastrectomy.

January 18, 2012 2:10 am

The gastric emptying is shorter after Duodenal Switch than after Sleeve Gastrectomy. This has been studied by having volunteers consume a known amount of measured food that contained trace amounts of medical nuclear markers. Using special imaging cameras, the amount of radiation collected in the stomach was measured over time. In the case of the Duodenal Switch patients, the emptying half time was 28 +/- 16 minutes, with the normal non-operated patient be at 91 +/- 20 minutes(i). The Gastric emptying after sleeve gastrectomy has been reported to be 38 +/- 19(ii) minutes and 57 +/-19(iii) minutes in two different studies.

(i) J. Hedberg et al., Gatric Emptying and Postprandial PYY resposnce after Biliopancreatic Diversion with Duodenal Switch. Obesity Surgery, (2001) 21:609-615.

(ii) Braghetto et al., Scintigraphic evaluation of gastric emptying in obese patients submitted to sleeve gastrectomy compared to normal subjects. Obesity Surgery, (2009); 19:1515-21

(iii) Bernstine et al. Gastric emptying is not affected by sleeve gastrectomy, without removal of the gastric antrum. Obesity Surgery, 2009;19:293-8.

Vitamin and Mineral Deficiencies

January 14, 2012 12:20 pm

Articles highlighting vitamin and mineral deficiencies after Duodenal Switch surgery.   Neurologic dysfunction and pancytopenia secondary to acquired copper deficiency following duodenal switch: case report and review of the literature.  Btaiche et al. Oct 2011 PubMed Abstract ABSTRACT: The duodenal switch (DS) procedure is a type of restrictive-malabsorptive bariatric surgery that is typically reserved for severe morbidly obese people (body mass index >50 kg/m(2)) with obesity-related comorbidities, when diet, lifestyle changes, and pharmacologic therapy fail to achieve adequate weight loss. Patients who undergo the DS procedure are at risk for malabsorption, malnutrition, and nutrient deficiencies. Copper deficiency is a commonly reported long-term complication of Roux-en-Y gastric bypass (RYGB) surgery. However, data are limited on copper deficiency-associated complications and their treatment in DS patients. This article presents a case of a patient who developed hypocupremia with associated pancytopenia, myeloneuropathy, and leukoencephalopathy following DS and reviews the literature related to the pathophysiology of copper deficiency and copper replacement in bariatric surgery patients. When severe diarrhea was present, intravenous elemental copper 4 mg (as cupric chloride)/d in addition to daily oral copper gluconate was necessary to correct the hypocupremia and improve the hematologic indices and neurologic symptoms of copper deficiency. When diarrhea subsided, oral elemental copper 4 mg (as copper gluconate) 3 times daily maintained normal serum copper concentrations and avoided the relapse of severe neurologic dysfunction. Regular monitoring of serum copper and ceruloplasmin concentrations is recommended following DS surgery to detect any copper deficiency before irreversible neurologic damage occurs. Long-term copper supplementation is likely necessary to maintain normal copper status in DS patients. Nutritional deficiencies in bariatric surgery patients: prevention, diagnosis and treatment.  Schweiger et al. Nov 2010 PubMed Abstract  ABSTRACT: The number of people suffering from surgery and obesity in the western world is constantly growing. In 1997 the World Health Organization (WHO) defined obesity as a plague and one of greatest public health hazards of our time. The National Institution of Health (NIH) declared that surgery is the only long-term solution for obesity. Today there are four different types of bariatric surgery. Each variation has different implications on the nutritional status of bariatric surgery patients. Bariatric surgery candidates are at risk of developing vitamin and mineral nutritional deficiencies in the post-operative stage, due to vomiting, decrease in food intake, food intolerance, diminution of gastric secretions and bypass of absorption area. It is easier and more efficient to treat nutritional deficiencies in the preoperative stage. Therefore, preoperative detection and correction are crucial. Blood tests before surgery to detect and treat nutritional deficiencies are crucial. In the postoperative period, blood tests should be conducted every 3 months in the first year after operation, every six months in the second year and annually thereafter. Multivitamin is recommended to prevent nutritional deficiencies in all bariatric surgery patients. Furthermore, iron, calcium, Vitamin D and B12 are additionally recommended for Roux-en-Y Gastric Bypass patients. Patients with Biliopancreatic diversion and Duodenal Switch should also take fat soluble vitamins. Zinc Deficiency: A Frequent and Underestimated Complication After Bariatric Surgery.  Sallé et al. Aug 2010 PubMed Abstract BACKGROUND: Although zinc deficiency is common after bariatric surgery, its incidence is underestimated. The objective was to monitor zinc and nutritional status before and 6, 12 and 24 months (M6, M12 and M24) after gastric bypass (Roux-en-Y gastric bypass), sleeve gastrectomy and biliopancreatic diversion with duodenal switch (DS) in patients receiving systematised nutritional care. METHODS: Data for 324 morbidly obese patients (mean body mass index 46.2 +/- 7.3 kg/m(2)) were reviewed retrospectively. The follow-up period was 6 months for 272 patients, 12 months for 175, and 24 months for 70. Anthropometric, dietary and serum albumin, prealbumin, zinc, iron and transferrin saturation measures were determined at each timepoint. RESULTS: Nine percent of patients had zinc deficiency pre-operatively. Zinc deficiency was present in 42.5% of the population at M12 and then remained stable. Zinc deficiency was significantly more frequent after DS, with a prevalence of 91.7% at M12. Between M0 and M6, variation in plasma prealbumin, surgery type and zinc supplementation explained 27.2% of the variance in plasma zinc concentration. Surgery type explained 22.1% of this variance between M0 and M24. Mean supplemental zinc intake was low (22 mg/day). The percentage of patients taking zinc supplementation at M6, M12 and M24 was 8.9%, 20.6% and 29%, respectively. CONCLUSIONS: Reduced protein intake, impaired zinc absorption and worsening compensatory mechanisms contribute to zinc deficiency. The mechanisms involved differ according to the type of surgery and time since surgery. Zinc supplementation is necessary early after bariatric surgery, but this requirement is often underestimated or is inadequate.   Vitamin status after bariatric surgery: a randomized study of gastric bypass and duodenal switch.  Aasheim et al. Jul 2009 PubMed Abstract  BACKGROUND: Bariatric surgery is widely performed to induce weight loss. OBJECTIVE: The objective was to examine changes in vitamin status after 2 bariatric surgical techniques. DESIGN: A randomized controlled trial was conducted in 2 Scandinavian hospitals. The subjects were 60 superobese patients [body mass index (BMI; in kg/m(2)): 50-60]. The surgical interventions were either laparoscopic Roux-en-Y gastric bypass or laparoscopic biliopancreatic diversion with duodenal switch. All patients received multivitamins, iron, calcium, and vitamin D supplements. Gastric bypass patients also received a vitamin B-12 substitute. The patients were examined before surgery and 6 wk, 6 mo, and 1 y after surgery. RESULTS: Of 60 surgically treated patients, 59 completed the follow-up. After surgery, duodenal switch patients had lower mean vitamin A and 25-hydroxyvitamin D concentrations and a steeper decline in thiamine concentrations than did the gastric bypass patients. Other vitamins (riboflavin, vitamin B-6, vitamin C, and vitamin E adjusted for serum lipids) did not change differently in the surgical groups, and concentrations were either stable or increased. Furthermore, duodenal switch patients had lower hemoglobin and total cholesterol concentrations and a lower BMI (mean reduction: 41% compared with 30%) than did gastric bypass patients 1 y after surgery. Additional dietary supplement use was more frequent among duodenal switch patients (55%) than among gastric bypass patients (26%). CONCLUSIONS: Compared with gastric bypass, duodenal switch may be associated with a greater risk of vitamin A and D deficiencies in the first year after surgery and of thiamine deficiency in the initial months after surgery. Patients who undergo these 2 surgical interventions may require different monitoring and supplementation regimens in the first year after surgery. This trial was registered at ClinicalTrials.gov as NCT00327912.  

Type 2 Diabetes Cure

January 14, 2012 9:22 am

Studies on Duodenal Switch as a type 2 diabetes cure.   Improvement of type 2 diabetes mellitus in obese and non-obese patients after the duodenal switch operation.  Frenken et al. Mar 2011 PubMed Abstract  Full PMC Article  ABSTRACT: Introduction. Type 2 diabetes mellitus (T2DM) is one of the most important obesity-related comorbidities. This study was undertaken to characterise the effect of the biliopancreatic diversion with duodenal switch (BPD-DS) in morbidly obese and nonmorbidly obese diabetic patients. Methods. Outcome of 74 obese diabetic patients after BPD-DS and 16 non-obese diabetic patients after BPD or gastric bypass surgery was evaluated. Insulin usage, HbA(1c)-levels, and index of HOMA-IR (homeostasis model assessment of insulin resistence) were measured. Results. A substantial fraction of patients is free of insulin and shows an improved insulin sensitivity early after the operation, another fraction gets free of insulin in a 12-month period after the operation and a small fraction of long-term insulin users will not get free of insulin but nevertheless shows an improved metabolic status (less insulin needed, normal HbA(1c)-levels). Conclusion. BPD-DS leads to an improvement of T2DM in obese and non-obese patients. Nevertheless, more data is needed to clarify indications and mechanisms of action and to adjust our operation techniques to the needs of non-obese diabetic patients. Metabolic intestinal bypass surgery for type 2 diabetes in patients with a BMI <35 kg/m2: comparative analysis of 16 patients undergoing either BPD, BPD-DS, or RYGB.  Frenken et al. Mar 2011 PubMed Abstract  BACKGROUND: Metabolic surgery for type 2 diabetes mellitus in patients with low body mass index (BMI) is a novel concept. Early studies show the surgery to be safe and effective but are inconclusive regarding the most effective procedure. METHODS: Metabolic intestinal bypass surgery was performed in n = 16 patients with type 2 diabetes and a BMI < 35 kg/m(2) (mean age 56 years, range 36-68; 8 females; mean BMI 32 kg /m(2), range 26-34.5). Biliopancreatic diversion with duodenal switch (BPD-DS), biliopancreatic diversion according to Scopinaro (BPD), and Roux-en-Y gastric bypass (RYGB) were performed in 7, 5, and 4 diabetic patients, respectively. Mean preoperative duration of medical antidiabetic therapy was 16 years (range 4-40). Thirteen patients used insulin on average for 6 years (range 1-12), the mean insulin requirement was 92 IU per day (range 30-140). The analysis was accomplished retrospectively from data prospectively collected in our data base. RESULTS: At discharge from hospital, only 3 of the 13 patients who used insulin preoperatively required small amounts of insulin (mean 21 IU per day, range 15-30) to keep fasting and postprandial plasma glucose levels below 200 mg/dl. After 1 year, none of the patients used insulin or oral antidiabetic drugs. The HbA1c level decreased for the total patient population from 8.6% (range 5.8-12.1) preoperatively to 6.0% (range 4.3-7.8), 5.7% (range 4.1-7.6), and 5.6% (range 4.1-7.8) after 3, 6, and 12 months, respectively. The HbA1c levels at 1 year were significantly lower after BPD-DS and BPD than after RYGB (5.2%, range 4.1-6.4 versus 6.7%, range 5.8-7.8, p < 0.01, DHbA1c 1.4%, 95% confidence interval 0.5-2.4). CONCLUSION: Metabolic intestinal bypass surgery for type 2 diabetes in low BMI patients is effective, with HbA1c levels at 1 year after the operation being significantly lower after BPD-DS or BPD than after RYGB. Biliopancreatic diversion with duodenal switch in patients with type 2 diabetes mellitus: is the chance of complete remission dependent on therapy and duration of insulin treatment?  Cho et al. Mar 2011 PubMed Abstract  BACKGROUND: Rapid resolution of type 2 diabetes mellitus (T2DM) is a common feature after intestinal bypass surgery bypassing the duodenum and parts of the jejunum. However, the parameters determining the individual chance of remission are imprecisely defined. METHODS: Biliopancreatic diversion with duodenal switch and sleeve gastrectomy (BPD-DS) was performed in n = 86 patients with T2DM (mean age 50 years, range 26-68, 51 females; BMI 47 kg/m(2), range 26-71). The patients were retrospectively divided into 4 groups according to the treatment modality and the duration of insulin treatment preoperatively: n = 18 patients were treated with oral antidiabetic drugs only (group 1); n = 32, n = 24, and n = 12 patients were treated with insulin for less than 5 years, for 5-10 years, and for more than 10 years (groups 2, 3, and 4), respectively. RESULTS: At discharge from hospital, all patients of groups 1 and 2 were free of insulin usage, 30% and 75% of the patients of groups 3 and 4 used up to 48 units of insulin per day (mean 24, n = 16). After 1 year, only 4 patients of group 4 permanently required small amounts of insulin (mean 17 units per day) to keep blood glucose below 200 mg/dl. These 4 patients had been using insulin preoperatively for 13, 15, 22, and 25 years. In 3 of these 4 patients, fasting C-peptide was measured and found to be low (<1.2 ng/ml). The rate of complete remission of diabetes for the whole study population was 91%. CONCLUSION: BPD-DS reliably causes rapid and complete remission of T2DM in all patients on oral antidiabetic drugs and in patients with insulin treatment for less than 5 years. In patients with insulin treatment longer than 5 or 10 years, complete remission rates decline to 88 and 66%, respectively. A low C-peptide preoperatively might be a specific adverse prognostic parameter for the chance of diabetes remission.   Bileopancreatic Diversion with Duodenal Switch Lowers Both Early and Late Phases of Glucose, Insulin and Proinsulin Responses After Meal.  Johansson et al. Mar 2010 PubMed Abstract   BACKGROUND: Hyperproinsulinemia is associated with obesity and type 2 diabetes. We explored the after-meal dynamics of proinsulin and insulin and postprandial effects on glucose and lipids in patients treated with bileopancreatic diversion with duodenal switch (BPD-DS) surgery compared with normal-weight controls [body mass index (BMI)+/-SD, 23.2 +/- 2.4 kg/m(2)]. METHODS: Ten previously morbidly obese (BMI+/-SD, 53.5 +/- 3.8 kg/m(2)) patients free from diabetes who had undergone BPD-DS (BMI+/-SD, 29.0 +/- 5.2 kg/m(2)) 2 years earlier were recruited. A standardised meal (2400 kJ) was ingested, and glucose, proinsulin, insulin, free fatty acids and triglycerides (TGs) were determined during 180 min. Follow-up characteristics yearly on glucose, lipids, creatinine and uric acid over 3 years after BPD-DS are presented. RESULTS: Fasting glucose and insulin were lower, 0.4 mmol/L and 4.6 pmol/L, respectively, in the BPD-DS group despite higher BMI. Fasting proinsulin was similar in both groups. Postprandial area under the curve (AUC) for glucose, proinsulin and insulin did not differ between the two groups (p = 0.106-734). Postprandial changes in glucose, proinsulin and insulin were essentially similar but absolute concentrations of proinsulin and insulin were lower in the later phases in the BPD-DS group (p = 0.052-0.001). Postprandial AUC for TGs was lower in the BPD-DS group (p = 0.005). Postprandial changes in TGs were lowered in the intermediate phase (p = 0.07-0.08) and in the late phase (0.002). Follow-up data showed markedly lowered creatinine and uric acid after BPD-DS. CONCLUSIONS: BPD-DS surgery induces a large weight loss and lowers, close to normal, postprandial responses of glucose, proinsulin and insulin but with marked lowering of TGs. Weight and type 2 diabetes after bariatric surgery: systematic review and meta-analysis.  Buchwald et al. Mar 2009 PubMed Abstract  Register to access the full article from The American Journal of Medicine   BACKGROUND: The prevalence of obesity-induced type 2 diabetes mellitus is increasing worldwide. The objective of this review and meta-analysis is to determine the impact of bariatric surgery on type 2 diabetes in association with the procedure performed and the weight reduction achieved. METHODS: The review includes all articles published in English from January 1, 1990, to April 30, 2006. RESULTS: The dataset includes 621 studies with 888 treatment arms and 135,246 patients; 103 treatment arms with 3188 patients reported on resolution of diabetes, that is, the resolution of the clinical and laboratory manifestations of type 2 diabetes. Nineteen studies with 43 treatment arms and 11,175 patients reported both weight loss and diabetes resolution separately for the 4070 diabetic patients in these studies. At baseline, the mean age was 40.2 years, body mass index was 47.9 kg/m2, 80% were female, and 10.5% had previous bariatric procedures. Meta-analysis of weight loss overall was 38.5 kg or 55.9% excess body weight loss. Overall, 78.1% of diabetic patients had complete resolution, and diabetes was improved or resolved in 86.6% of patients. Weight loss and diabetes resolution were greatest for patients undergoing biliopancreatic diversion/duodenal switch, followed by gastric bypass, and least for banding procedures. Insulin levels declined significantly postoperatively, as did hemoglobin A1c and fasting glucose values. Weight and diabetes parameters showed little difference at less than 2 years and at 2 years or more. CONCLUSION: The clinical and laboratory manifestations of type 2 diabetes are resolved or improved in the greater majority of patients after bariatric surgery; these responses are more pronounced in procedures associated with a greater percentage of excess body weight loss and is maintained for 2 years or more. Is Type 2 Diabetes an Operable Intestinal Disease? A Provocative Yet Reasonable Hypothesis  Rubino Feb 2008 PubMed Abstract  Full article can be found at Diabetes Care  Type 2 diabetes, which accounts for 90-95% of all cases of diabetes, is a growing epidemic that places a severe burden on health care systems, especially in developing countries. Because of both the scale of the problem and the current epidemic growth of diabetes, it is a priority to find new approaches to better understand and treat this disease. Gastrointestinal surgery may provide new opportunities in the fight against diabetes. Conventional gastrointestinal operations for morbid obesity have been shown to dramatically improve type 2 diabetes, resulting in normal blood glucose and glycosylated hemoglobin levels, with discontinuation of all diabetes-related medications. Return to euglycemia and normal insulin levels are observed within days after surgery, suggesting that weight loss alone cannot entirely explain why surgery improves diabetes. Recent experimental studies point toward the rearrangement of gastrointestinal anatomy as a primary mediator of the surgical control of diabetes, suggesting a role of the small bowel in the pathophysiology of the disease. This article presents available evidence in support of the hypothesis that type 2 diabetes may be an operable disease characterized by a component of intestinal dysfunction. Duodenal switch without gastric resection: results and observations after 6 years.  Cossu et al. Nov-Dec 2004 PubMed Abstract  BACKGROUND: The results on metabolic effects of the classical biliopancreatic diversion (BPD) have led us to investigate the operation without gastric resection, thus preserving stomach and pylorus, in patients who are not seriously obese but suffer from hypercholesterolemia, often associated with type 2 diabetes and hypertriglyceridemia. METHODS: Between 1996 and 1999, we performed the duodenal switch (DS) without gastric resection on 24 mildly obese patients. Mean preoperative BMI was 36.2 kg/m(2). 17 patients (70.8%) suffered from type 1 diabetes, 4 (16.6%) had impaired glucose tolerance, while the remainder had fasting hyperglycemia. In 20 patients (83.3%), hypercholesterolemia and alterations in lipid profile were present. Another 20 patients were taking drugs for arterial hypertension. The pluri-metabolic syndrome was present in 41.6% of patients. RESULTS: Mean follow-up was 4 years. BMI reduction and weight loss were not large. 2 patients who had severe longstanding diabetes type 2 needed a second operation of the classical BPD because of failure in improving diabetes. Another 2 patients were changed to classical BPD because of a relapsing chronic duodeno-ileal ulcer. The incidence of ileal ulcer was 29.1%. Regarding hypercholesterolemia, hypertrigliceridemia, and type 2 diabetes when there is a good pancreatic “reservoir”, the operation seems effective in the long-term. Protein absorption is better than that obtained with the classical BPD. CONCLUSIONS: Our long-term results suggest that in carefully selected patients suffering from serious hypercholesterolemia or type 2 diabetes with insulin reserves still at an acceptable level, and with BMI 30-40, DS without gastric resection can be proposed as a surgical treatment for metabolic diseases but not for obesity.

Nutritional Deficiencies

January 14, 2012 8:23 am

Clinical data that discusses nutritional deficiencies in post-op Duodenal Switch patients. Metabolic changes after morbid obesity surgery using the duodenal switch technique. Long term follow-up.  Vázquez et al. Dec 2011 PubMed Abstract INTRODUCTION: The duodenal switch (DS) technique is considered to be complex surgery with a series of metabolic complications due to its malabsorptive character. For these reasons, it has not been extensively used by bariatric surgeons. Despite this, we consider it to be a suitable technique for the grossly obese. PATIENTS AND METHODS: A retrospective study was performed on 110 patients with morbid obesity operated on using the DS technique and who were followed up for a minimum period of four years after surgery. We evaluated the weight loss, the outcomes of the comorbidities, and the metabolic complications. RESULTS: The loss of excess weight was greater than 50% in 75% of the patients after 12 months follow up. The comorbidities suffered by 68 patients (75.5%) were completely resolved. The most frequent metabolic complications were iron (Fe) deficiency and an increased parathyroid hormone (PTH). CONCLUSION: DS is a safe and effective technique for the treatment of morbid obesity, with good weight loss results, a high percentage of remission of the comorbidities, a similar morbidity and mortality to other techniques, and with correctable nutritional changes, and thus acceptable.   Obesity surgery results depending on technique performed: long-term outcome.  Gracia et al. April 2009 PubMed Abstract  BACKGROUND: Many techniques have excellent results at 2 years of follow-up but some matters regarding their long-term efficacy have arisen. This is why bariatric surgery results must be analyzed in long-term follow-up. The aim of this study was to extend the analysis over 5 years, evaluating weight loss, morbidity, and mortality of the surgical procedures performed. METHODS: This was a retrospective cohort study of the different procedures for morbid obesity practiced in our Department of Surgery for morbid obesity. The results have been analyzed in terms of weight loss, morbidity improvement, and postoperative morbidity (Bariatric Analysis And Reporting Outcome System). RESULTS: One hundred twenty-five patients were operated on open vertical banded gastroplasty (VBG), 150 patients of open biliopancreatic diversion (BPD) of Scopinaro, 100 patients of open modified BPD (common limb 75 cm; alimentary limb 225 cm), and 115 patients of laparoscopic Roux-en-Y gastric bypass (LRYGBP). Mean follow-up was: VBG 12 years, BPD 7 years, and LRYGBP 4 years. An excellent initial weight loss was observed at the end of the second year of follow-up in all techniques, but from this time an important regain of weight was observed in VBG group and a discrete weight regain in LRYGBP group. Only BPD groups kept excellent weight results so far in time. Mortality was: VBG 1.6%, BPD 1.2%, and LRYGBP 0%. Early postoperative complications were: VBG 25%, BPD 20.4%, and LRYGBP 20%. Late postoperative morbidity was: protein malnutrition 11% in Scopinaro BPD, 3% in Modified BPD group, and no cases reported either in VBG group or LRYGBP group; iron deficiency 20% VBG, 62% Scopinaro BPD, 40% modified BPD, and 30.5% LRYGBP. A 14.5% of VBG group required revision surgery to gastric bypass or to BPD due to 100% weight regain or vomiting. A 3.2% of Scopinaro BPD with severe protein malnutrition required revision surgery to lengthen common limb to 100 cm. A 0.8% of LRYGBP required revision surgery to distal LRYGBP (common limb 75 cm) due to 100% weight regain. CONCLUSIONS: The most complex bariatric procedures increase the effectiveness but unfortunately they also increase morbidity and mortality. LRYGBP is safe and effective for the treatment of morbid obesity. Modified BPD (75-225 cm) can be considered for the treatment of superobesity (body mass index > 50 kg/m(2)), and restrictive procedures such as VBG should only be performed in well-selected patients due to high rates of failure in long-term follow-up.   Roux-en-Y gastric bypass versus a variant of biliopancreatic diversion in a non-superobese population: prospective comparison of the efficacy and the incidence of metabolic deficiencies.  Skroubis et al. April 2006 PubMed Abstract  BACKGROUND: In the non-superobese population, an agreement has not been made as to the optimal bariatric operation. The present study reports the results of a prospective comparison of Roux-en-Y gastric bypass (RYGBP) and a variant of biliopancreatic diversion (BPD) in a non-superobese population. METHODS: From a cohort of 130 patients with BMI 35 to 50 kg/m(2), 65 patients were randomly selected to undergo RYGBP and 65 to undergo BPD. All patients underwent complete follow-up evaluation at 1, 3, 6, and 12 months postoperatively and every year thereafter. RESULTS: Patients in both groups have completed their second postoperative year. Mean % excess weight loss (%EWL) was significantly better after BPD at all time periods (12 months, P=0.0001 and 24 months, P=0.0003), and the %EWL was >50% in all BPD patients compared to 88.7% in the RYGBP patients at 2-year follow-up. No statistically significant differences were observed between the 2 groups in early and late non-metabolic complications. Hypoalbuminemia occurred in only 1 patient (1.5%) after RYGBP and in 6 patients after BPD (9.2%). Only 1 patient from each group was hospitalized and received total parenteral nutrition. Glucose intolerance, hypercholesterolemia, hypertriglyceridemia and sleep apnea completely resolved in all patients in both groups, although mean total cholesterol level was significantly lower in BPD patients at the second year follow-up (t-test, P<0.0001). Diabetes completely resolved in all BPD patients and in 7 of the 10 diabetic RYGBP patients. CONCLUSION: Both RYGBP and BPD were safe and effective procedures when offered to non-superobese patients. Weight loss after BPD was consistently better than that after RYGBP, as was the resolution of diabetes and hypercholesterolemia. Because the nutritional deficiencies that occurred following this type of BPD were not severe and were not significantly different between the 2 operations, both may be offered to non-superobese patients, keeping in mind the severity and type of preoperative co-morbidities as well as the desired weight loss. Nutritional Markers following Duodenal Switch for Morbid Obesity  Rabkin et al. Jan 2004 PubMed Abstract  Full Article  BACKGROUND: Laparoscopic duodenal switch with gastric reduction (LapDS) is a minimally invasive hybrid operation combining moderate intake restriction with moderate malabsorption for treatment of morbid obesity. In LapDS, both the quantity of food ingested and the efficiency of digestion are reduced. METHODS: A cohort of 589 sequential LapDS patients had laboratory studies drawn annually. Serum markers for calcium, iron and protein metabolism and for hepatic function were analyzed using SAS statistical software. RESULTS: There were 95 men and 494 women. Mean age was 44 years, mean BMI 50 kg/m(2) and mean preoperative weight 142 kg. Although mean hemoglobin decreased below reference and mean parathyroid hormone (PTH) increased above reference, similar to abnormal values reported after Roux-en-y gastric bypass, both hemoglobin and calcium in LapDS readily returned to within the reference range following supplementation with iron and calcium respectively. Mean iron, corrected calcium, alkaline phosphatase, albumin, total protein, aspartate aminotransferase (AST), alanine transaminase (ALT), and bilirubin remained within the normal range. CONCLUSION: LapDS is not associated with broad nutritional deficiencies. Annual laboratory studies, which are required following any type of bariatric operation, appear to be sufficient to identify unfavorable trends. In selected patients, additional iron and calcium supplementation are effective when indicated. Comparison of nutritional deficiencies after Roux-en-Y gastric bypass and after biliopancreatic diversion with Roux-en-Y gastric bypass.  Skroubis et al. Aug 2002 PubMed Abstract  BACKGROUND: Patients undergoing either Roux-en-Y gastric bypass (RYGBP) or biliopancreatic diversion (BPD) with RYGBP are at risk of developing metabolic sequelae secondary to malabsorption. We compared the differences in nutritional complications between these two bariatric operations. METHODS: A retrospective analysis of a prospective database was done. From June 1994 to December 2001, 243 morbidly obese patients underwent various bariatric procedures at our institution. Of these patients, 79 (BMI 45.6 +/- SD = 4.9) who underwent RYGBP (gastric pouch 15 +/- 5 ml, biliopancreatic limb 60-80 cm, alimentary limb 80-100 cm and common limb the remainder of the small intestine), and 95 super obese (BMI 57.2 +/- 6.1) who underwent a BPD (gastric pouch 15 +/- 5 ml, biliopancreatic limb 150-200 cm, common limb 100 cm and alimentary limb the remainder of the small intestine), were selected and studied for the incidence of micronutrient deficiencies and level of serum albumin at yearly intervals postoperatively. A variety of nutritional parameters including Hb, Fe, ferritin, folic acid, vitamin B12 and serum albumin were measured preoperatively and compared postoperatively at 1, 3, 6, 12, 18 and 24 months, and yearly thereafter. RESULTS: Nutritional parameters were compared preoperatively and at similar periods postoperatively. No statistically significant (P < 0.05) difference in the occurrence of deficiency was observed between the groups for any of the nutritional parameters studied, except for ferritin, which showed a significant difference at the 2-year follow-up (37.7% low ferritin levels after RYGBP vs. 15.2% after BPD, P = 0.0294). All of these deficiencies were mild, without clinical symptomatology and were easily corrected with additional supplementation of the deficient micronutrient, with no need for hospitalization. Regarding serum albumin, there was only one patient with a level below 3 g/dl in the RYGBP group and two in the BPD group. These three patients were hospitalized and received total parenteral nutrition for 3 weeks, without further complications. CONCLUSION: There was no significant difference in the incidence of deficiency of the nutritional parameters studied, except for ferritin, following RYGBP vs. BPD with RYGBP. The most common deficiencies encountered were of iron and vitamin B12. The incidence of hypoalbuminemia was negligible in both groups, with mean values above 4 g/dl.